Category: Peyronie’s Disease

A curved penis can often be helped without surgery. These articles explain Peyronie’s disease, the research on injections and traction, and the step-by-step protocol we use with the Priapus Shot® to help men become straighter, harder, and bigger.

  • JCPM2025.05.20 | Peyronie’s Disease | Scleroderma | PRF vs. PRP

    Journal Club with Pearls & Marketing 2025.05.20                   Cellular Medicine Association

    JCPM2025.05.20

    The following is an edited transcript of the Journal Club with Pearls & Marketing (JCPM) of May 20, 2025, with Charles Runels, MD.  

    >-> The PDF of this live journal club can be seen here <-<

    Topics Covered

    • PRP vs. PRF
    • Why Cleft Palate Repair Matters Even if You Only Care for Adult Women
    • PRP to Help with Chemotherapy
    • PRP Derived Exosomes for Wounds
    • When to Go With the Flow (and the Physician as a Person)
    • O-Shot® for Scleroderma
    • P-Shot® Procedure for Peyronie’s Disease
    • Here’s an Email You Could Send
    • References
    • Useful Links
    Charles Runels, MD
    Charles Runels, MD

    Charles Runels, MD
    Author, researcher, and inventor of the Vampire Facelift®, Orchid Shot® (O-Shot®), Priapus Shot® (P-Shot®), Priapus Toxin®, Vampire Breast Lift®, and Vampire Wing Lift®, & Clitoxin® procedures.

    Transcript

    Welcome to our Journal Club.

    We have two very good, landmark, supportive papers of what we do and others of interest.

    Especially if you’re doing the P-Shot® or the O-Shot® procedures, you’re going to find today very encouraging.

    PRP vs. PRF

    In this first paper, I get so many questions about PRP versus PRF, and I include it here because of those questions.[1] 

    Dr. Runels Botulinum Blastoff Course cover

    I like for us to think about all the different ideas. And part of the advantage of our group is that we are modifying our procedures as new science comes out and as our members think of new techniques. The dentistry profession was doing PRP at least a decade before we were with the idea that they had often hard to heal tissue with poor vascularization. And so they, out of necessity, went looking for ways to help with their surgery. And those in the GYN and the urology and facial plastic surgery space didn’t have to deal with that.

    So when I first picked up platelet-rich plasma in 2010, early 2010 when it was starting to make its way into cosmetic medicine, but not yet into sexual medicine, when I would speak with a dentist or veterinarians or even equestrians, they knew all about platelet-rich plasma. And the sports medicine people knew and the athletes knew, but most gynecologists did not know what it was about.

    For example, I taught a class up in Maine near the L.L. Bean store, and there was a lady who showed up as a model and she said, “Oh, we’ve been using this in our horses for years. So yes, I see what it does. I want an O-Shot®.”

    And so I like watching the dental research because they are a decade ahead of us. They quit wondering if platelet-rich plasma does anything and they’re more focused on the variations that might be used to make it work better.

    So I’m putting this here and it’ll be in the handouts when I shut down the meeting today. But clinically, my advantage of course is that I’m listening to our 2000-plus members and I’m hearing multiple problems arising when PRF is used with our procedures.

    => Apply for Online Training for Multiple PRP Procedures <=

    I’m still of the mind that PRF is more useful in wound care than in an O-Shot® or a P-Shot® or even cosmetic medicine.

    Problems with PRF

    One of our providers had a near miss with some signs of vascular occlusion when he put PRF in the lip and was able to recover circulation. But there were a few moments there of worry. And we don’t see that with PRP.

    It’s the same with the P-Shot®. I’ve received multiple emails from both patients and doctors describing problems with PRF that we don’t see with PRP.

    =>Next Hands-On Workshops with Live Models<=

    I’m not saying we don’t keep track of it, and I’m not saying there’s not usefulness in it, but so far I think if you’re doing P-Shots® or O-Shots® especially, and also for the Vampire Facelift®, I think you’re better off sticking with PRP instead of PRF.

    And I concede that at least something I say today will be proven wrong and absolutely wrong sometime in the future. But that’s what I’m seeing from the research, and I wanted you to have that.

    Why Cleft Palate Repair Matters Even if You Only Care for Adult Women

    Most of us don’t do cleft palate repair, but this is another paper that talks about how useful PRP is in that situation.[2] 

    And the reason I like these papers, even for those who are not doing facial plastic surgery, is of course we have similar problems when you’re treating an episiotomy scar or scarring of any kind: for example, the chronic sclerosis and scarring that happens with lichen sclerosus, in some ways Peyronie’s disease is remodeling a scar, and then sometimes we’re just treating scars where someone had an umbilical piercing or a surgical scar. I’ve treated basal cell scars from skin grafts, zoster scars, and of course acne scars.

    So I think it’s encouraging to see these papers come out that support that idea of using PRP to help with scars. I think one of the hindrances to medical progress is people, all of us, especially me, I try to force myself not to do this, but being caught in our fish tank, so to speak. And we’re looking at the research in our arena and not noticing other arenas.

    Of course, the same thing happens in business. So often the people who are successful in business just take an idea that’s succeeded in a different kind of business and just drag it over into theirs. When I started doing PRP in the genitalia, I was just treating the genitalia with the same idea that if causes neovascularization and neurogenesis and scar remodeling in the face, then it should happen with the scarring and vascular problems that happen in the vagina and the penis. And turns out that was a useful direction to go in. So having these papers, even if you’re not doing cleft palate repair, I think, is reassuring.

    PRP to Help with Chemotherapy

    This one, again, I don’t have as much of a direct usefulness for it too, but I’ve not seen anything in this category before: PRP for the side effects of chemotherapy.[3] 

    The effect of autologous cytokine-rich serum and platelet-rich plasma on oxidative status minerals and pro-inflammatory cytokines in the brain and serum and cyclophosphamide-induced ovarian failure. They took rats and they injected PRP and they documented: PRP therapies from the patient’s own blood have a potential as supportive or chemopreventive strategies with reduced side effects and treatment costs.

    So this is so early on, I’m not sure what to do with it, but I wanted us to be aware of it. And especially since we have so many types of physicians and some of you’re treating cancer, I wanted this on our radar so that some of you will actually come up with some good ideas. I think the fun thing that happens, as I just mentioned, is if you have your toe in two different arenas, then you might see things that others don’t see looking just in their fishbowl.

    Our variable backgrounds makes us able to come up with ideas that seem plain to one and not obvious to the other, I think that’s part of what happened with our Clitoxin® idea by having almost two decades of history of treating migraines and cosmetic use of botulinum toxin and thinking about how it might be working and reading that literature, and it became more obvious that it might be helpful for orgasm and sexual function in women when thinking about the feedback loops.[4] 

    And had I been sticking strictly to gynecology and didn’t have that two-decade history, it wouldn’t have been so obvious.

    Again, some of you are doing oncology, and you’ll think of ways to use this information that would never occur to me. So I just wanted to put it out there.

    PRP Derived Exosomes for Wounds

    And then a lot of you are talking about exosomes, so I wanted to show you this other paper. When I hear people talk about exosomes, to me it still feels even more misunderstood or poorly defined or ill-defined, I guess. Vaguely defined. More vaguely defined even than PRP because exosomes, are they homologous? Are they plant-based? Are they non-homologous or excuse me, autologous? Are they autologous, non-autologous, plant-based? Where are they coming from?

    => Apply for Online Training for Multiple PRP Procedures <=

    So they looked here at PRP and PRP-derived exosomes in wound healing.[5] 

    Some of you are using a source of exosomes that uses autologously derived exosomes with an outside processing company, and some of you are using plant-based exosomes that are something different. I think that the literature is leaning towards this strategy. Some of you are doing something called the Super Shot®, finding other ways to enhance the effects of our platelet-rich plasma.

    I don’t buy into the idea that if you’re over a certain age, your PRP is not at all effective, else if you did surgery, the skin wouldn’t heal. You couldn’t do a cholecystectomy on an 80-year-old. But I do agree that we need to keep looking for ways to enhance what we’re doing. And there’s an infinite number of variables.

    If you look on PubMed, there are now over 18,000 papers that come up if you put platelet-rich plasma in the search bar. When I first started doing and thinking about PRP in 2010, there were about 5,000.

     And already this year, we’re not halfway through the year, but we have half as many studies as we did last year. So there is a non-linear increase in the amount of research that’s being done. I think being tagged into our group and helping think about it, you are truly part of a revolution where regenerative therapies are not only becoming commonly done, but they’re becoming part of the standard protocols, but yet there’s still great need for understanding infinite number of variabilities in which they could be done.

    So this is just something to look at. I am still not doing exosomes when I do my O-Shot® and P-Shot® and I am getting great results, but I know some of you’re using it for hair or using it in place of PRP. I haven’t seen a study.

    The bottom line is the verdict is still out about we don’t have an answer about which actually works the best. And so I’m sticking with what I know has worked for over now almost a decade and a half, but keeping track of the rest of it.

    When to Go With the Flow

    I spoke with one of our providers and she says, “Everybody wants PRF now with their Vampire Facial®.” Okay, if you’re smearing it on the face and microneedling, does it really matter? They sell something on TikTok and that’s what they want. You just give it to them. It’s okay? But if you try to squirt that through a needle into the clitoris, then I think it’s a different thing. So sometimes you have to go with what they’re thinking.

    There was an old mentor of mine back in the days of medical school in the eighties who said, “Always try to integrate….” Actually, it was also in the book called The Physician Himself, which was written in 1882, said that you always try to integrate into your therapies what the patient wants.

    If they think that somehow taking vitamin C and smearing gravel from the street on their ear lobe will help their otitis media and you don’t see any harm to it, then you include it. Many things that were in the health food store, at which physicians scoffed, are now are prescription drugs.

    =>Next Hands-On Workshops with Live Models<=

    I try to integrate what I can without doing harm, without increasing expense if a patient wants something. And so yeah, I think it’s perfectly acceptable to use PRF if someone saw that on TikTok. But I think when you start trying to squirt it into the lip or the clitoris, you’re risking complications.

    O-Shot® for Scleroderma

    Okay, this one I brought out just because I have now heard even more people talk about our O-Shot® helping scleroderma. Of course, this is nanofat for cutaneous fibrosis and scleroderma, and they talk about using it in that instance, but it’s more support for what we’re seeing, which is that when you have someone coming to you for dyspareunia and dryness and the things that happen with scleroderma with female sexual function, it’s a indirect support of that.[6] We need more studies. If you want a low-hanging fruit, do a study and inject 50 women with dyspareunia and scleroderma and just do our regular O-Shot® and you’ll have a landmark study. But this would be support for that study.

    P-Shot® Procedure for Peyronie’s Disease

    I saved the best for last. They treated Peyronie’s disease and rapidly showed improvement with the injection of PRP.[7] And when they say rapid, this is rapid. If you remember the first study that I know of that came out about using our P-Shot® techniques for Peyronie’s disease was from Ronald Virag, out of Paris.[8] He was treating patients every once a week for six weeks. And these people just got treated three times.

    And so it went, first injection and then after two weeks, second injection, four weeks, and four weeks after the third injection, they measured. So they’re going not a long time. And the penile curvature, the plaque size, all improved.

    This one, they did not show improvement in erectile function that was statistical. If you look, here was the score.

    If you remember, our P-Shot® full effect is not until 12 weeks. So it was really early on for the neovascularization and neurogenesis, but there was still rapid plaque resolution with improvement. And there was no complications like are common with Xiaflex with penile fracture. So the side effect was a slight but not statistical improvement in erectile dysfunction, which is a good thing. They’d used an Angel systems, so it was a double spin centrifuge and they did inject the plaque.

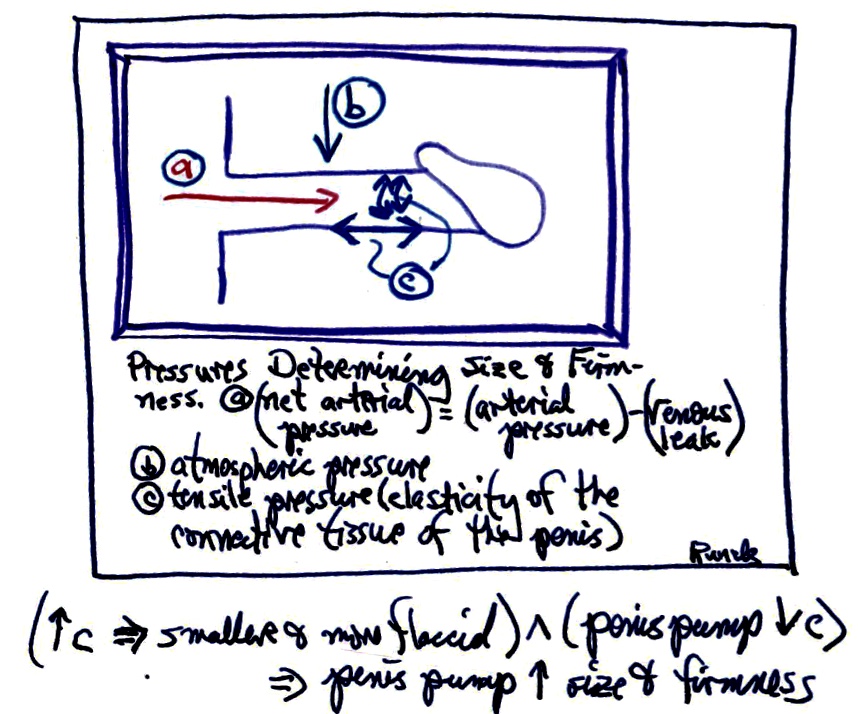
    Now, many people in our group, some of them very high-volume injectors, are just doing a regular P-Shot® and combining it with the pump and seeing excellent results.

    You can palpate the plaque. So it’s not a big deal to do a regular P-Shot®, save a CC and just inject as if you were trying to inject intradermally. So when your needle goes into that plaque, you can feel it’s hard to push. So if you puncture it a few times and inject as you’re going through it, you can feel it. You don’t need an ultrasound. You can feel it. But for that, you will need to do a block. Otherwise, it’s tormenting.

    Even though they didn’t do it in this study, of course, because it would involve more than one variable and make it harder to reach statistical conclusions, we, as part of our protocol, combine the P-Shot® with a vacuum pump.

    In one study in the British Journal of Urology, 51% of men canceled their surgery just using the pump for 10 minutes a day for 12 weeks.[9] 

    And I spoke with Ronald Virag. We were at a meeting in Venice and I shared the podium with him. And he said, yes, in his study, he just used platelet-rich plasma. He used Regen, which is a single spin. But in clinical practice he combines it with a vacuum pump. I’ll show it to you. For the full protocol that I’m recommending, and until we have enough research to change it, can be found here<=

    If I’m treating someone for Peyronie’s, I send them to this page and tell them, “Do everything on the page.”

    The page includes a little video. I’ll have to add this paper, but includes links to the research supporting the ideas of what we’re doing.

    The seven-step plan talks about the pump, and there’s a link to the research. We actually have studies showing that CoQ10 and vitamin E that dose improve results.

    And then I have a protocol here. 

    Do the P-Shot®, wait six weeks. I think when you’re looking at the wound care studies, they’re usually separated by eight to 12 weeks. So if you’re pushing them that close together a week or two apart, you get results more quickly for your research paper, but if you are trying to preserve the patient’s time and money, it could be that if you separated it by six weeks, you’ll find what many of us have found, six to eight weeks, that they often don’t need a second or a third shot. They’re happy with it. So those are suggested timeframes between the injections.

    Low testosterone is associated with Peyronie’s. Adding testosterone hasn’t been shown to treat it, I don’t think. But because it’s associated, replace it.

    And then these others have more to do with erectile function. And again, aerobic fitness or VO2 max is associated with Peyronie’s disease, having low aerobic capacity, as is smoking. And not just with increased blood flow.

    There are some physiological reasons why Cialis every day could help not just the erection, but with resolution of Peyronie’s.

    So that’s the seven-step process. I’ll add this paper to the research.

    Here’s an Email You Could Send

    Remember, people don’t really care about an ad, but they like to read letters from you that include news. Because it’s news, if you are a P-Shot® provider, you could send them an email that talks about this new research and offer to help them (if you are not a P-Shot® provider, you can apply for online training here< ). Here’s a quick way to do get the email done:

    1. Copy and paste the following message into a new Word document.
    2. Then edit it so that it sounds like you.
    3. Add a story or a personal observation if you have time.
    4. Then, fill in the information with your phone number, etc., and send it to your patients.

    Hello,

    Peyronie’s disease (a bending of the male genitalia) can be very serious and damage a marriage and the psychological well-being of man. New research just came out showing that using our P-Shot® ideas, you can improve male function and correct the curvature that can be so damaging to a family.

    Even better, it is truly shocking how fast it works.

    Here’s the research<=

    Here’s more about the whole protocol<=

    And you can see the side effects were none except for a slight increase in function. That was not statistic at this short interval.

    Also exciting, instead of risking the genitalia fracture that happens with Xiaflex (which is no longer approved for use in Canada, Europe, Japan, or Australia). And if you paid cash for Xiaflex, it would be a series of injections that would cost $27,000. Our procedure costs much less and has never caused a penile fracture.

    If you think this may help you or someone you love, please contact us.

    Sincerely,

    (your name)
    (your picture)
    (your website)
    (your phone number)
    (your email address)

    ____________________________________

    And as always, I offer people their money back if they’re not delighted.

    I know that frightens some people, but when you have a procedure that works the vast majority of the time, you still come out good.

    If you already know the patient and they’re familiar to you, let’s say that you’re their family practice doctor, you’ve already talked about the erectile dysfunction, I made a slight modification in the pricing. In that case, you could do that first injection for 997 or a thousand bucks if you want. But for a new patient coming in, you have to spend time with that person. And there’s going to be no insurance reimbursement if you’re all cash practice. And remember, the massage therapist gets 350 bucks for a six-month course. And you have to spin blood. You have cost of goods and your time. So 1800 is a very good price. It’s less than a new set of tires.

    But if you wanted to drop it for one of your current patients whom you already know, that would be okay. And we all do things for free, but we should all be advertising and telling people over the phone those prices so we’re not competing on price.

    And of course, if you add in our new ideas with Priapus Toxin® and putting a hundred units of Xeomin or some botulinum toxin similar into the penis along with your PRP, that would help with erectile dysfunction or could help as the studies show.[10] [11] [12] [13] [14]

    And that would be extra cost. I think that should be somewhere around an extra a thousand dollars to do that, a thousand to 1500, more if you’re in a town where it costs more money to turn on the lights. Let’s see. I think that’s all the questions, I think, and we come in right at 30 minutes. So hopefully that was helpful to you. Thank you for being here. See you next week.

    => Apply for Online Training for Multiple PRP Procedures <=

    =>Next Hands-On Workshops with Live Models<=

    References

    Acerra, Alfonso, Mario Caggiano, Andrea Chiacchio, Bruno Scognamiglio, and Francesco D’Ambrosio. “PRF and PRP in Dentistry: An Umbrella Review.” Journal of Clinical Medicine 14, no. 9 (May 6, 2025): 3224. https://doi.org/10.3390/jcm14093224.

    Dachille, Giuseppe, Andrea Panunzio, Leonardo Bizzotto, Maria Valeria D’Agostino, Federico Greco, Giuseppe Guglielmi, Umberto Carbonara, et al. “Platelet-Rich Plasma Intra-Plaque Injections Rapidly Reduce Penile Curvature and Improve Sexual Function in Peyronie’s Disease Patients: Results from a Prospective Large-Cohort Study.” World Journal of Urology 43, no. 1 (May 15, 2025): 306. https://doi.org/10.1007/s00345-025-05691-5.

    Elsamna, Samer T., Fayssal Alqudrah, Mahnoor Khan, Teagen Smith, Jon Robitschek, and Julia Toman. “Platelet Rich Products in Cleft Palate Repair.” The Cleft Palate Craniofacial Journal, May 16, 2025, 10556656251342003. https://doi.org/10.1177/10556656251342003.

    El-Shaer, Waleed, Hussein Ghanem, Tamer Diab, Ahmed Abo-Taleb, and Wael Kandeel. “Intra-Cavernous Injection of BOTOX® (50 and 100 Units) for Treatment of Vasculogenic Erectile Dysfunction: Randomized Controlled Trial.” Andrology 9, no. 4 (2021): 1166–75. https://doi.org/10.1111/andr.13010.

    Ermiş, Mustafa, Erol Karakaş, Hanifi Erol, Gökhan Akcakavak, Recai Aci, Furkan Ümit, Özhan Karatas, and Gülay Çiftci. “Effect of Autologous Cytokine-Rich Serum and Platelet-Rich Plasma Administration on Oxidative Status, Minerals and Proinflammatory Cytokines in Brain and Serum in Cyclophosphamide-Induced Ovarian Failure.” Journal of Molecular Histology 56, no. 3 (May 19, 2025): 159. https://doi.org/10.1007/s10735-025-10448-w.

    Giuliano, Francois, Pierre Denys, and Charles Joussain. “Effectiveness and Safety of Intracavernosal IncobotulinumtoxinA (Xeomin®) 100 U as an Add-on Therapy to Standard Pharmacological Treatment for Difficult-to-Treat Erectile Dysfunction: A Case Series.” Toxins 14, no. 4 (April 16, 2022): 286. https://doi.org/10.3390/toxins14040286.

    Habashy, Engy, and Tobias S. Köhler. “Botox for Erectile Dysfunction.” The Journal of Sexual Medicine 19, no. 7 (July 2022): 1061–63. https://doi.org/10.1016/j.jsxm.2022.03.216.

    He, Ling, Nan Zhao, Xiaoling Chen, Wenjie Zhang, Kun Lv, and Yuanhong Xu. “Platelet-Rich Plasma-Derived Exosomes Accelerate the Healing of Diabetic Foot Ulcers by Promoting Macrophage Polarization toward the M2 Phenotype.” Clinical and Experimental Medicine 25, no. 1 (May 15, 2025): 163. https://doi.org/10.1007/s10238-025-01651-w.

    Porter, Dr Mark. “Botox: The New Viagra? It’s One Way to Treat Erectile Dysfunction,” sec. times2. Accessed November 8, 2022. https://www.thetimes.co.uk/article/botox-could-help-men-beat-erectile-dysfunction-here-s-what-to-know-8x2vvt9c7.

    Raheem, Amr Abdel, Giulio Garaffa, Tarek Abdel Raheem, Michelle Dixon, Amanda Kayes, Nim Christopher, and David Ralph. “The Role of Vacuum Pump Therapy to Mechanically Straighten the Penis in Peyronie’s Disease.” BJU International 106, no. 8 (2010): 1178–80. https://doi.org/10.1111/j.1464-410X.2010.09365.x.

    Runels, Charles, and Alexandra Runnels. “The Clitoral Injection of IncobotulinumtoxinA for the Improvement of Arousal, Orgasm & Sexual Satisfaction- A Specific Method and the Effects on Women.” Journal of Women’s Health Care 13, no. 3 No. 715 (March 20, 2024). https://doi.org/10.35248/2167-0420.24.13.715.

    Shehri, Zaed Ghassan, Issam Alkhouri, Mohammad Y Hajeer, Ibrahim Haddad, and Mohamad Husam Abu Hawa. “Evaluation of the Efficacy of Low-Dose Botulinum Toxin Injection Into the Masseter Muscle for the Treatment of Nocturnal Bruxism: A Randomized Controlled Clinical Trial.” Cureus, December 4, 2022. https://doi.org/10.7759/cureus.32180.

    Toro, Giuseppe Di, Angelo Alito, Giulia Leonardi, Fiorenza Giulia Di Toro, and Simona Portaro. “Nanofat and Lipofilling for Cutaneous Fibrosis in Scleroderma: Current Evidence and Future Directions,” n.d.

    Virag, Ronald, Hélène Sussman, Sandrine Lambion, and Valérie de Fourmestraux. “Evaluation of the Benefit of Using a Combination of Autologous Platelet Rich-Plasma and Hyaluronic Acid for the Treatment of Peyronie’s Disease.” Sexual Health Issues 1, no. 1 (2017). https://doi.org/10.15761/SHI.1000102.

    Tags

    P-Shot®, O-Shot®, PRP, PRF, platelet-rich plasma, Peyronie’s disease, erectile dysfunction, scleroderma, dyspareunia, cleft palate, wound healing, sexual medicine, cosmetic medicine, exosomes, regenerative medicine, PRP vs PRF, platelet-rich fibrin, PRP side effects, penile curvature, vacuum pump, Priapus Shot®, Vampire Facial®, Angel system, double spin centrifuge, Xiaflex alternatives, neurogenesis, neovascularization, autologous serum, cytokines, oxidative stress, chemotherapy side effects, facial plastic surgery, scar treatment, lichen sclerosis, episiotomy scars, acne scars, botulinum toxin, Priapus Toxin®, sexual function, testosterone, CoQ10, vitamin E, aerobic fitness, VO2 max, smoking and ED, PRP pricing, PRP injection protocol, regenerative protocols, PRP research, PRP in oncology, PRP and scleroderma, PRP complications, PRP enhancements, PRP marketing strategies, PRP for hair, autologous exosomes, Charles Runels

    Helpful Links

    => Next Hands-On Workshops with Live Models <=

    => Dr. Runels Botulinum Blastoff Course <=

    => The Cellular Medicine Association (who we are) <=

    => Apply for Online Training for Multiple PRP Procedures <=

    => FSFI Online Administrator and Calculator <=

    => 5-Notes Expert System for Doctors <=

    => Help with Logging into Membership Websites <=

    => The software I use to send emails: ONTRAPORT (free trial) <= 

    => Sell O-Shot® products: You make 10% with links you place; shipped by the manufacturer), this explains and here’s where to apply <=

    Charles Runels, MD             888-920-5311              CellularMedicineAssociation.org

    Page  of


    [1] Acerra et al., “PRF and PRP in Dentistry.”

    [2] Elsamna et al., “Platelet Rich Products in Cleft Palate Repair.”

    [3] Ermiş et al., “Effect of Autologous Cytokine-Rich Serum and Platelet-Rich Plasma Administration on Oxidative Status, Minerals and Proinflammatory Cytokines in Brain and Serum in Cyclophosphamide-Induced Ovarian Failure.”

    [4] Runels and Runnels, “The Clitoral Injection of IncobotulinumtoxinA for the Improvement of Arousal, Orgasm & Sexual Satisfaction- A Specific Method and the Effects on Women.”

    [5] He et al., “Platelet-Rich Plasma-Derived Exosomes Accelerate the Healing of Diabetic Foot Ulcers by Promoting Macrophage Polarization toward the M2 Phenotype.”

    [6] Toro et al., “Nanofat and Lipofilling for Cutaneous Fibrosis in Scleroderma: Current Evidence and Future Directions.”

    [7] Dachille et al., “Platelet-Rich Plasma Intra-Plaque Injections Rapidly Reduce Penile Curvature and Improve Sexual Function in Peyronie’s Disease Patients.”

    [8] Virag et al., “Evaluation of the Benefit of Using a Combination of Autologous Platelet Rich-Plasma and Hyaluronic Acid for the Treatment of Peyronie’s Disease.”

    [9] Raheem et al., “The Role of Vacuum Pump Therapy to Mechanically Straighten the Penis in Peyronie’s Disease.”

    [10] Porter, “Botox.”

    [11] Habashy and Köhler, “Botox for Erectile Dysfunction.”

    [12] Shehri et al., “Evaluation of the Efficacy of Low-Dose Botulinum Toxin Injection Into the Masseter Muscle for the Treatment of Nocturnal Bruxism.”

    [13] Giuliano, Denys, and Joussain, “Effectiveness and Safety of Intracavernosal IncobotulinumtoxinA (Xeomin®) 100 U as an Add-on Therapy to Standard Pharmacological Treatment for Difficult-to-Treat Erectile Dysfunction.”

    [14] El-Shaer et al., “Intra-Cavernous Injection of BOTOX® (50 and 100 Units) for Treatment of Vasculogenic Erectile Dysfunction.”

    What is the Priapus Shot® (P-Shot®)?
    See the research on the P-Shot®

  • The Latest Research on Drugs that Treat Peyronie’s Disease

    This video reviews a 2021 paper in Expert Review of Clinical Pharmacology on the medications used to treat Peyronie’s disease and their limitations. Research on the Priapus Shot® procedure for Peyronie’s is linked below.

    Read the research/review about drugs to treat Peyronie’s

    Research supporting the Priapus Shot® procedure for treating Peyronie’s disease


    What is the Priapus Shot® (P-Shot®)?
    Find a P-Shot® provider near you
    See the research on the P-Shot®

  • Injections for Peyronie’s Disease. Research Review

    This video reviews a 2021 systematic review in Sexual Medicine Reviews on injection treatments for Peyronie’s disease, including less common forms of the condition. Research on the Priapus Shot® procedure for Peyronie’s is linked below.

    Find Priapus Shot® Provider<–

    Read the Research Review<—

    Read research about the Priapus Shot® for treating Peyronie’s

    More research about the Priapus Shot®<–

    What is the Priapus Shot® (P-Shot®)?

  • How to treat Peyronie’ s without surgery (new research)

    See review of the research here<–
    And more here<–
    Find nearest certified provider<–
    Apply to become a provider of the Priapus Shot® procedure<–

    IMPORTANT:  The natural progression of Peyronie’s Disease is that it gets worse with time. In other words, if you have Peyronie’s disease and you do nothing, it often worsens with time.

    If you look at the research, though most of the people treated with Priapus Shot® methods got better, some did not get better and some got worse.  The fact that most got better and some got worse does NOT mean conclusively that the procedure made them worse since the disease usually gets worse when left untreated.  Sometimes the Priapus Shot® just does not work and so the disease progresses.  We wish it worked every time in every person –but it does not.

    If your Peyronie’s disease gets worse, after any treatment, most likely it got worse because you have Peyronie’s and that’s what Peyronie’s disease does…the procedure did not work for you. But, your doctor didn’t give you Peyronie’s disease and most likely he/she did not make you worse–the disease did.

    On the other hand, no procedure is without risk and it could be that there are risks to the Priapus Shot® that are unknown to us and/or that occur more frequently than we suspect.  You always have the option to not be treated at all or to choose another treatment.  However, surgery and Xiaflex have their own risks.  Here’s the possibilities with Xiaflex (click to read)<– 

    Dr. Ronald Virag showed that PRP works better and with fewer side effects that Xiaflex (and with less serious side effects), but in the end THERE IS NO PERFECT PROCEDURE.

    Still, we think that the Priapus Shot® is worth trying before going to more other methods (one of the risks of the Priapus Shot® can be that you get a better/harder erection).

    If you do choose to do the Priapus Shot®–after discussion with your physician–we recommend you use the following protocol to increase the chances of your success (click)<–

    Cellular Medicine Association
    1-888-920-5311

    What is the Priapus Shot® (P-Shot®)?

  • Peryronie’s Disease Personal Video Story from Brave Man

    Brave Man Tells His Story about Treatment of Peyronie’s Disease with the Priapus Shot® [P-Shot®] Procedure
    *Results May Vary*

    Transcript

    Meet Dr. Shanthala<–

    Dr. Shanthala Shivananjappa
    Dr. Shanthala Shivananjappa


    Doug Brown: Hi, I’m Doug Brown. I’m here at Dr. Shanthala, MD’s office, and I’m here to have a procedure for something that most men or most people don’t even understand, which is called Peyronie’s disease.

    Peyronie’s is a condition that happens over time for most men, and quite frankly it’s a little embarrassing. But it’s where the penis actually starts to have a curvature to it, and it happens gradually over time. And many men are embarrassed by it and many men don’t understand what it’s all about because it’s happening and they’re trying to figure out, well, why is this happening to me? That’s what was happening, as well, to myself.

    And so I was seeking out multiple treatments, and, frankly, there wasn’t a lot that I could find online, at the time. And then I would find things of, you know, magic potions and magic pills, and those wouldn’t work, and different types of contraptions that people wanted to sell.

    I eventually decided that I was going to just take the medical route, and so I went and had a couple of injections of what they call Xiaflex, and Xiaflex is kind of an enzyme that eats away. What happens is plaque gets underneath the skin. It’s due to either an injury or sometimes an allergic reaction, it’s really kind of what the medical community calls idiopathic. It’s really not a cause that somebody really understands why this happens.

    And it’s been interesting to me because, you know, now that I’ve had the issue and I’ve talked to other people, and they now know they have the issue, but they didn’t even know what it was, so as I was progressing through this process with the Xiaflex, I actually got some results.

    The Xiaflex are a series of injections. However, they’re very, very costly. Too little vials of medication are actually $9,000 from the pharmacy, and so I had a couple of those, but then the insurance wouldn’t support it any longer. So I was looking for other alternatives, because even though I got some results from it, I wanted more of a natural type of process. Because while I went through those, I had things called hematoma, which is where the blood vessels sort of burst with inside the skin, or it felt like that anyways, and things would swell. And it was very painful.

    Anyways, I’m here because I went through what is called the P-shot. And the P-shot is a process where they use your own natural blood and what they call PRP, I believe it’s called, and what that does is it goes in and it actually does a similar thing that the Xiaflex does. However, it’s not a series of multiple injections that you have to go through, and there’s no adverse reaction to it.

    So I had one done already, and immediately I started noticing a vast change, and for the positive. So, where the curve was still a good sized curve, it started straightening out immediately on all angles. And so it’s been very successful for me, and so I’m back to have another one, because I got better results this time, the first time, and I want to have better results the second time.

    So the good thing about the PRP and the P-shot versus the Xiaflex, for myself, was not only do you not have to have insurance get involved, but number two, it’s very quick. So the time recovery on the P-shot versus the Xiaflex shot, the recovery time was instantaneous. Really, that day. It wasn’t painful after that. It was very straightforward.

    But with the Xiaflex, you do it in one day and then you got to wait a couple of days and you go back again, and they’re constantly … I’ll just, for the lack of better terms, using an invasive type of process, and so there is a week to four week recovery time. And what I noticed with the P-shot was the recovery time was instantaneous. I was recovered that day, and back to normal function.

    And so, you know, I’m here to talk about this because most men, frankly, they don’t want to talk about it. It’s kind of embarrassing to them. And, you know, this happens to a lot more men than people know.

    So I’m here to answer a series of questions as well, so there may be some questions thrown to me at this point.

    Speaker 2: Well, Doug, thank you very much for talking. I appreciate it. Very well said. I was just wondering, does this hurt? Do you have any pain when you’re having the procedure done?

    Doug Brown: No, I mean, because they’re numbing up the area, you do feel a slight pinch when the needle is inserted, but it’s not painful. At least it wasn’t for me. And I don’t think it’s anything worse than what I would consider maybe a mosquito bite or a bite like that.

    And then once the pinch is gone, I didn’t feel a thing, honestly.

    Speaker 2: How many shots do you think would be optimal to get the results that you desire?

    Doug Brown: Well, I think it depends on the person’s condition. You know, I’ve talked to men who have slight curvature, and unfortunately, the more curvature that one has, then it’s a challenge with all kinds of function, whether it’s sexual function or also urinary function as well. I was running into that in the beginning. And that’s one of the reasons I just said … you know, I didn’t know about the P-shot before, so I just went to the Xiaflex ’cause that was the only thing that medical doctors who are traditionalists would recommend.

    So, you know, I got results in my first P-shot, so for me, I’m back because I want more results, but I noticed an immediate straightening and I noticed an immediate … I used to have an indenture on both sides where the curvature was happening, and they both went away within an hour. You know, I was like, wow, what happened. And now, the reason I’m back is because over time the indenture on the left is completely gone and the one on the right is slightly back, so I want to get rid of that as well.

    The other thing that I noticed immediately, I noticed a size increase immediately. So length and girth, width, as well. So, you know, for me, it was pretty immediate. But I think most men probably should look, you know, between one and four treatments, probably on average, to make it work out right.

    And the reality is, when you compare it against the other, even with co-pays on insurance, what I have found is this is much more economical, and the recovery time … I mean, the second Xiaflex shot I had, I mean, it took me about four weeks to recover. So, and you know, it was painful for about two weeks.

    Speaker 2: Did you feel that you had your privacy respected when you came into the office?

    Doug Brown: Here?

    Speaker 2: Yes, yes.

    Doug Brown: Oh, yeah, absolutely. Yeah, they’re … you know, I’m kind of a, like, you know, I’m not really that modest anyways. Probably one of the reasons I’d be willing to do this and that. But I do understand that many men, you know, in different professions, and I sort of have a public persona profession so to do this is actually a stretch for me, but I think it’s so important that, you know, a lot of men, or a lot of guys out there, they’re suffering with this condition and, you know, it’s affecting their whole life. It was affecting my whole life. And I think that the privacy here was respected as well as anywhere I’ve ever been. In fact, better so.

    What I got here is, you know, in the other medical community, because they’re dealing with insurance companies and they’re running people through the mill and they’ve got such a high overhead on a lot of things, there wasn’t, I would say, that personalization that I got here, by any means.

    You know, sometimes I would have to wait an hour to get in for the procedure on the other place, or, you know, a couple of times the doctor was so busy because they were out on call all night long, they were sleeping, they couldn’t even get back to the office, so I had to go back a couple of times. And it was and hour drive for me, because there’s not a lot of people who actually do this type of treatment, and so, you know, certainly, it’s more far and few between.

    So when I found this, and I found it in my local area, I was like, you know what, I’m going to give it a shot, and I’m very grateful I did.

    Research supporting the use of the P-Shot® for Peyronie’s disease (and how it works better then Xiapex)<–

    More research supporting the above man’s  brave story<–

    The full P-Shot® protocol for the treatment of Peyronie’s Disease<–

    Find nearest P-Shot® provider<–

    Apply to become provider of the Priapus Shot® [P-Shot®] procedure<–

    What is the Priapus Shot® (P-Shot®)?

  • When Should You Treat Peyronie’s with the P-Shot® Procedure…Early After Onset, or Later?

    Question (name changed)…

    Dr. Runels:

    I’m an ENT doctor but in this case a urology pt with recent-onset (noticed 2-3 weeks ago) Peyronie’s. My urologist ______ in ______ gave me your flier about the Priapus Shot® treatment.

    (1) Does your Rx address the plaques?

    (2) Does it stop or reverse the Peyronie’s process?

    (3) Is it better to treat early (now) or wait 8-10 months when the plaques stabilize?

    Thank you.

    Answer:

    (1) Yes! Research shows a decrease in plaque size.
    (see research listing below)

    (2) If you mean, does the Priapus Shot® procedure help the curvature? Yes, in most men.  If you mean, does it permanently reverse the underlying process so the curvature never recurs…then probably in some. To further elaborate with some data, we did the following research (click to read) with lichen sclerosus (also thought to be an autoimmune process, like Peyronie’s), showing that our process with the O-Shot® procedure decreased inflammation according to 2 blinded dermatopothologists–indicating that somehow the procedure down-regulates the autoimmune response.  There are other papers showing this downregulation of the autoimmune process by PRP.

    Further as to permanence, our provider group has seen women who see a recurrence of their lichen at 1 year out, a few who are not helped at all, and many who are still well at 3-4 years post procedure. How these data will relate to Peyronie’s disease remains to be seen but we expect a similar spectrum.
    (see research listing below)

    (3) DEFINITELY  better to treat early  before the scar tissue matures. I saw Dr. Virag lecture in Venice this past summer when we shared the podium and he will soon publish data showing that using PRP is more effective and safer than Xiaflex. Depending on how you look at the data, Xiaflex has a 1 in 50 to 1 in 100 risk of fracture/impotence post procedure. The Priapus Shot® procedure has associated with it the probable side effect of an improvement in erection quality by around 5 – 7 on the 25 point scale commonly used.
    (see research listing below)

    IMPORTANT! If your provider is not on the following list of physicians who have studied the accepted methods of the Priapus Shot® procedure (click) and agreed to follow them, then your physician may be a wonderful provider, but I have no way of knowing who or how he/she was trained and what method he learned. So, I have NO way to make any comments about the quality of the procedure he/she may provide. What I can say, is that your physician (if she/he says he’s providing the P-Shot® but is not listed on that directory) is either knowingly or unknowingly breaking the law and pretending to be part of a group that he/she is NOT a part of. The certified providers of the Priapus Shot® procedure share notes with each other, finance research, and support the advancement of the effectiveness of the procedure. THOSE WHO USE THE NAME “PRIAPUS SHOT” BUT WHO ARE NOT LISTED AS ONE OF OUR MEMBERS ARE USING THE FRUITS OF OUR LABORS ILLEGALLY and possibly providing and inferior service by deceiving patients.

    Certified Members of the Priapus Shot® Provider Group (click)<–
    Research Listings for the Priapus Shot® Protocol for Treating Peyronie’s Disease (click to read)<–

    Best regards,

    Charles Runels, MD
    Charles Runels, MD


    Inventor of the Priapus Shot® Procedure


  • Straighter, Harder, Bigger. Step 3. Priapus Shot®

    Straighter, Harder, Bigger. Step 3. Priapus Shot®

    Priapus Shot® Procedure

    The Priapus Shot® procedure indicates a specific way of treating the penis with blood-derived growth factors extracted from the man’s own blood (autologous). Some people call these blood-derived growth factors platelet-rich plasma (PRP) but there may be growth factors in plasma we don’t yet know about that do not come from the platelets. The name “Priapus Shot®” is registered with the US Patent & Trademark office as a “service mark” to protect patients by indicating a specific protocol. The name is not a synonym for the injection of blood in to the penis—such a definition would not be specific enough to indicate any particular quality of care. and so would not warrant protection as intellectual property.

    The trademark defines a specific method of that providers agree to follow and develop; this agreement offers quality control and is followed and developed by over 500 urologists, interventional radiologists, family practitioners, and internists in multiple countries and by faculty in medical schools where further studies are being done.

    The Priapus Shot® procedure protocol also involves patient selection, patient evaluation & education (including explanation of consent), preparation of the PRP, local anesthesia, PRP injection, post injection use of a penis pump on a daily basis, and a daily dose of tadalafil (in come men). Other post injection steps can include: stopping smoking, CoQ10 (12), vitamin E (13), Trimix, and aerobic exercise. Protocol steps vary depending on the patient and those variations also comprise the Priapus Shot® protocol.

    Patient selection includes identifying those who may need hormonal treatment, or family counseling, or vascular surgery, as well as those who may have co-morbidities or who may be taking drugs that interfere with sexual function. Some patients are not treated with the Priapus Shot® protocol because another treatment or no treatment is more appropriate.

    The policy of most of our providers of the procedure offers a complete refund to any man who is not happy with the Priapus Shot® procedure.

    Consulting with the patient includes informing him that unexpected side effects could occur and the results will vary with some patients seeing no benefit. Antibiotics fail in 1 in 5 people in the hospital with pneumonia—resulting in death. Antibiotics “work” but do not work for all people. The same can be said for most all procedures including the Priapus Shot procedure.

    The preparation of the PRP involves a device approved by the FDA for isolating PRP from whole blood for autologous use. Since blood is not a drug, it is not governed by the FDA but the devices used to isolate PRP for injection back into the body are regulated by the FDA. Multiple kits have gained FDA approval. Some of the approved kits include Regen, Magellan, TruPRP, Eclipse, Pure Spin, Harvest, & Emcyte. There are over 8,000 research papers on pub med discussing the science of PRP, and not one serious side effect has been documented when FDA approved kits were used to prepare the PRP.

    Most men find the procedure very comfortable if a topical lidocaine cream is applied to the penis about 15 minutes prior to the procedure. A very small needle (1/2 inches long, 30 gauge) needle is used for the injection. However, some men do ask for a dorsal nerve block which can easily be done using 2% lidocaine for a near painless procedure (this same block can be used for prosthesis placement—so it makes a 30 gauge needle completely painless for most men.

    The Science

    An early report that PRP may be useful in the penis appeared in a paper published in Urology in 2003 mentioning that, in animal models, using blood-derived growth factors injected into the penis successfully treated erectile dysfunction and also mentioned that such a strategy may be feasible in men— actually providing a way to correct the underlying pathology (1). In contrast, Viagra and Trimix do not correct the underlying pathology of decreased penile circulation.

    Another animal study in 2010 showed that transferring adipocyte derived stem cells (ADSCs) into the penis caused endothelia cell growth (new blood flow) as well as increased nitric oxide activity in the dorsal nerve (harder erection). But, the ADSCs were tagged before injection (to keep up with them) and most of the injected stem cells died! So the improvement seen was not from maturation of the ADSCs but rather from recruitment and activation by growth factors of stem cells already in the body—indicating PRP may demonstrate a similar effect (2).

    Dr. Virag (also a pioneer of Trimix injections) published research demonstrating improvement in erectile function, size, and correction of Peyronie’s disease with the use of PRP. His studies both published (and to be published) demonstrate a mean increase of 7 on the ED Intensity Score when PRP is injected into the plaque and into the corpus cavernosum of the human penis (3).

    Find Certified Priapus Shot® Provider (click)<==

    One of the growth factors found in PRP (over 20 known) includes vascular endothelial growth factor (VEGF). In one animal study, the animals were castrated causing a shutting off of testosterone to create a penis that demonstrated, on microscopy, atrophy of smooth muscle and nerves as well as endothelial cell pathology. Then another group received VEGF injections directly into the corpus cavernosum along with castration. VEGF injection into the penis at the time of castration prevented the atrophy as effectively as did testosterone replacement. Moreover, VEGF reversed cavernosoetric findings of leakage (4).

    The above studies and others not cited indicate an improvement in the health, circulation, and strength (density) of penile tissue with injection of blood-derived growth factors into the penis.

    What Goes with the Shot?

    In regards to improvement in erection firmness, the Priapus Shot® protocol also includes a recommendation of aerobic exercise which by meta analysis of 5 randomized controlled studies using the Erectile Function Scale showed an increase of 5 (5,6).

    As previously stated, the complete Priapus Shot® protocol, also includes the use of a penis pump, which as a stand-alone therapy has been demonstrated to improve erection both as part of a penile rehabilitation program as well as an adjunct to other therapies (7,8).

    This same penis pump strategy, even without the PRP, has been demonstrated to increase penis size by 2-3 cm, while traction (another physical therapy that can be included as part of the Priapus Shot® protocol) was shown to increase penis length by 1.5-2.5 cm (8, 9). Adding PRP to the protocol shows improved results according to data collected by urologists currently utilizing the Priapus Shot® protocol (to be presented). The 2.5 cm improvement seen with the penis pump alone is in the 10-20% growth range for the average sized penis. As previously stated, while patient results vary, any patients that are not happy with the procedure are given a complete refund.

    Ultrasound studies of humans, post treatment, by Dr. Virag and by other physicians who offer the Priapus Shot® protocol demonstrate improved blood flow, an increase in endothelium (improved health), and decreased plaque size. Dr. Joseph Banno of Chicago recently presented a paper showing the Priapus Shot® procedure decreased venous leak as well as increased intra-penile arterial pressure.

    Dr. Virag’s studies, using the injection of PRP as a stand-alone (without physical therapies), also demonstrate improvement in the angle of the penis in men suffering with Peyronie’s disease (3). Also, strict adherence to a penis pump regimen is part of the Priapus Shot® protocol and the pump alone improves the angle significantly in over one-half of those studied in one study in the British Journal of Urology (10). This same study demonstrated growth of the penis using the pump alone (without the PRP injection). The PRP alone, in Dr Virag’s study, out-performed the pump with demonstration of remodeling of the plaque. I recommend using both methods: vacuum pump and Priapus Shot®.

    Studies show that the non-surgical treatment of Peyronie’s is most effective when a synergy of multiple modalities is engaged (11). So, the Priapus Shot® procedure includes the injection of PRP (demonstrated effective by Dr. Virag) combined with daily physical therapy using a penis pump for ten minutes twice a day and a daily low-dose of taladafil. Other modalities in the Priapus Shot® procedure that have been demonstrated to be synergistic include the following: stopping smoking, CoQ10 (12), vitamin E (13), trimix, and aerobic exercise. Such strategies are not intended to take the place of surgical correction or of the use of chemical surgery with collagenase—but rather to offer the man suffering with Peyronie’s disease the optimal non-surgical treatment as a first step with surgery reserved if non-surgical therapies fail.

    The penis pump alone (part of the Priapus Shot® protocol) has been shown to improve the effectiveness of Cialis and of Trimix injections (8). We are seeing men decrease the dosage of Viagra and/or Trimix by about 50 percent when the complete Priapus Shot® protocol is used. The Priapus Shot® protocol does not intend to make any particular therapy obsolete (including surgery) but rather to offer a protocol for enhancing an overall, synergistic approach to correcting penile pathology. However the surgical treatment of Peyronie’s disease can be unsatisfying and lead to serious complications (14); we (the Priapus Shot® providers) are seeing the safety profile of PRP and the Priapus Shot® protocol as offering an appealing conservative and often effective step to take before proceeding to surgery. The risk from PRP is certainly much less than for surgery and less than for collagenase—offering another reason to start with the Priapus Shot® when treating Peyronie’s or erectile dysfunction.

    Apply for Certification as Priapus Shot® Provider (click)<==

    When considering the duration of effectiveness of the Priapus Shot® procedure and risks involved, you may find it helpful to consider the nature of the cell biology employed. A review article considering the basic science of PRP discusses the fact that the autologous growth factors are exactly what’s generated to propagate healing should the man have surgery. The healing peptides, chemotactic factors, and pluripotent stem cells employed are exactly what’s generated by the normal healing process and offers no inherent risk for infection or allergy (16).

    In over 8,000 papers published about PRP on pub med, there is not one serious sequelae reported that I can identify (multiple review articles address safety). This seems logical when you consider the material being injected is autologous and normally produced to help healing and to fight infection.

    Wound care studies demonstrate the nature of multiple tissue types being regenerated (with no reported risk of neoplasia in multiple biopsy studies (17-20).

    Moreover, in rat studies (where biopsy of the dorsal nerve is feasible), PRP has been shown to help regenerate nerve tissue and restore erectile function when prostate surgery is modeled with crush injury to the dorsal nerve (21,22). Some studies of stem cell therapies demonstrate that the stem cells do not actually mature into healthy tissue but rather signal for the improvement of the involved ganglion and nerve conduction by recruitment of stem cells to the area – exactly what happens with PRP.

    Stem cells are not directly prepared as part of the Priapus Shot® procedure, but we are seeing similar results as what’s reported with stem cell studies. Stem Cell studies often use PRP as a carrier for the stem cells, bringing into question which is the active agent (23-24).

    The idea of safety is further emphasized by the literature indicating that not only are there no reports of serious allergic reactions to PRP, but research also shows that PRP can attenuate the autoimmune response. One split-scalp study (with placebo control) showed improvement in alopecia areata, with the use of PRP, that out-performed triamcinolone (25). Another study using PRP in the genitalia of women, showed improvement in lichen sclerosus as determined by both patient survey and by 2 blinded dermatopathologists (26). This attribute of PRP (attenuation of the autoimmune response) could partly explain the effectiveness of the Priapus Shot® protocol for the treatment of both Peyronie’s disease and erectile dysfunction since Peyronie’s is thought to be partly caused by an autoimmune response.

    Hard & Easy Cases

    Hard Cases

    • Penis Growth-Only 60% of men achieve 1/2 inches or more in growth (circumference and length). But, men in that 60% sometimes see up to 1.5 inches in circumference & length (often after 2 to 3 procedures).
    • Men with long-standing vascular disease see less response. If the blood flow going to the penis (ileac arteries) is blocked, then the Priapus Shot® injection into the penis will not help much. The man needs a vascular surgeon. One way to get an idea here….if the man sees absolutely no response when taking Viagra or Cialis for more than 2 years, then he may have blockages or other problems that the Priapus Shot will not help.

    Easy Cases

    • Post op for prostate surgery as part of a penile rehabilitation program. If the man could achieve erection before the surgery, the following the Priapus Shot® protocol could be very beneficial (even if it’s been 2 or 3 years since surgery).
    • Improved firmness of erection in the man who can already achieve erection. Typical results are that he may be able to cut the dose of Viagra or Trimix in half (but still need the drug) or if he needs only a low dose of the drugs he may be able to stop using them.
    • Improvement in lichen sclerosus. This is HUGE since lichen sclerosus appears on the foreskin with severe discomfort and often recurs even if the man has a circumcision.
    • Peyronie’s Disease. This possibility is another HUGE benefit of the procedure—with the Priapus Shot® probably safer and more effective than collagenase injections (research to be published soon). If a man undergoes surgery for Peyronie’s disease, the curvature often recurs later since the autoimmune process continues. Also, with surgery, there can be infection and shortening of the penis. None of those side effects have been seen with the Priapus Shot® procedure (side effects include INCREASE in size in most men with Peyronie’s).

    Summary

    In summary, multiple studies support the idea that blood-derived growth factors (when prepared in a proper way using a kit approved by the FDA for the preparation of PRP), as used in the Priapus Shot® protocol, support the health and function of the penis. Erectile dysfunction is associated with anhedonia, and successful treatment leads to better function, better relationships, and more pleasure in life (27).

    Hope you find this helpful!

    Peace & health,

    Charles Runels, MD
    Inventor of the Priapus Shot® Procedure

    Apply for Certification as Priapus Shot® Provider (click)<==

    Find Certified Priapus Shot® Provider (click)<==

    References

    1. Siroky M. Vasculogenic erectile dysfunction: newere therapeutic strategies. J Urol. 2003;170(2 Pt 2):S24-9.

    2. Garcia MM, Fandel TM, Lin G, Shindel AW, Banie L, LinC-S, and Lue TF. Treatment of erectile dysfunction in the obese type 2 diabetic ZDF rat with adipose tissue-derived stem cells. J Sex Med 2010;7:89–98

    3. Virag R. A New Treatment of Lapeyronie’s Disease by Local Injections of Plasma Rich Platelets (PRP) and Hyaluronic Acid. Preliminary Results. e-mémoires de l’Académie Nationale de Chirurgie. 2014;13(3):96-100.

    4. Rogers R. Intracavernosal vascular endothelial growth factor (VEGF) injection and adeno-associated virus-mediated VEGF gene therapy prevent and reverse venogenic erectile dysfunction in rats. International Journal of Impotence Research. 2003;15:S24-9.

    5. Lamina S, Agbanusi E, Nwacha RC. Effects of Aerobic Exercise in the Management of Erectile Dysfunction: A Meta Analysis Study on Randomized Controlled Trials. Ethiopian Journal of Health Sciences. 2011;21(3):195-201.

    6. Esposito K, Giugliano F, Di Palo C, et al. Effect of Lifestyle Changes on Erectile Dysfunction in Obese Men: A Randomized Controlled Trial. JAMA. 2004;291(24):2978-2984. doi:10.1001/jama.291.24.2978.

    7. Nikolai S. Erection rehabilitation following prostatectomy–current strategies and future directions. Nature Reviews Urology. 2016;13(.):216-225.

    8. Pahlajani G,Raina R, Jones S, Ali M, and Zippe C. Vacuum erection devices revisited: Its emerging role in the treatment of erectile dysfunction and early penile rehabilitation following prostate cancer therapy. J Sex Med 2012;9:1182–1189.

    9. Sellers T, Dineen M, Wilson SK. Vacuum protocol and cylinders that lengthen allow implantation of longer, inflatable prosthesis. Toronto, ON: (Abst) Society of Sexual Medicine; 2008.

    10. Raheem A. The role of vacuum pump therapy to mechanically straighten the penis in Peyronie’s disease. BJU Int.. 2016;117(4):E7.

    11. Levine L. Peyronie’s disease: contemporary review of non-surgical treatment. Transl. Androl. Urol. 2013;2(1):39-44.

    12. Safarinejad M. Safety and efficacy of coenzyme Q10 supplementation in early chronic Peyronie’s disease: a double-blind, placebo-controlled randomized study. International Journal of Impotence Research. 2010;22(5):298-309.

    13. Paulis G. Efficacy of vitamin E in the conservative treatment of Peyronie’s disease: legend or reality? A controlled study of 70 cases. Andrology. 2013;1(1):120-128.

    14. Lue T. The Challenges of Peyronie’s disease. Translational Andrology & Urology. 2012;1(S1):PS 9.

    15. Raynor M. Dorsal Penile Nerve Block Prior to Inflatable Penile Prosthesis Placement: A Randomized, Placebo‐Controlled Trial. The Journal of Sexual Medicine. 2012;9(11):2975-2979.

    16. Sanchez-Gonzales J. Platelet-Rich Plasma Peptides: Key for Regeneration. International Journal of Peptides. 2012;10:1-10.

    17. Taylor D. A systematic review of the use of platelet-rich plasma in sports medicine as a new treatment for tendon and ligament injuries.. Clin J Sport Med. 2011;21(4):344-52.

    18. Yuan T, Zhang C-Q, Wang JH-C. Augmenting tendon and ligament repair with platelet-rich plasma (PRP). Muscles, Ligaments and Tendons Journal. 2013;3(3):139-149.

    19. Sell S. A case report on the use of sustained release platelet-rich plasma for the treatment of chronic pressure ulcers. The Journal of Spinal Cord Medicine. 2011;34(1):122-7.

    20. Conde-Montero, E., Horcajada-Reales, C., Clavo, P., Delgado-Sillero, I. and Suárez-Fernández, R. (2014), Neuropathic ulcers in leprosy treated with intralesional platelet-rich plasma. Int Wound J. doi:10.1111/iwj.12359

    21. Ding X. The effect of platelet-rich plasma on cavernous nerve regeneration in a rat model.. Asian J Androl. 2009;11(2):215-21.

    22. Ding X. Platelet-rich plasma on the Cavernous Nerve Regeneration. Chinese Medical journal. 2008;88(36):2578-2580.

    23. Rene’ Y. Safety of Intracavernous Bone Marrow-Mononuclear Cells for Postradical Prostatectomy Erectile Dysfunction: An Open Dose-Escalation Pilot Study. European Urology. 2016;69(6):988-991.

    24. Fandel T. Recruitment of Intracavernously Injected Adipose-Derived Stem Cells to the Major Pelvic Ganglion Improves Erectile Function in a Rat Model of Cavernous Nerve Injury. European Urology. 2012;61(1):201-210.

    25. Singh S. Role of platelet-rich plasma in chronic alopecia areata: Our centre experience.. Indian Journal of Plastic Surgery. 2015;48(1):57-9.

    26. Goldstein A. ISSVD 2015 Abstracts. Autologous Platelet Rich Plasma (PRP) Intradermal Injections for the Treatment of Vulvar Lichen Sclerosus. Journal of Lower Genital Tract Disease. 2015;19(3):S1-S25.

    27. Goldstein A., Runels C. Intradermal Injection of autologous platelet-rich plasma for the treatment of vulvar Lichen sclerosus. Journal of the American Academy of Dermatology. 2017;76(1):158-160

    27. Zaman H. Association of psychological factors, patients’ knowledge, and management among patients with erectile dysfunction. Patient Preference and Adherence. 2016;10:807.

    Save

    Save

  • Peyronie’s & ED Treatment: The Priapus Shot® Procedure

    Priapus Shot® Procedure

    The Priapus Shot® procedure indicates a specific protocol for treating the penis with blood-derived growth factors: specifically platelet-rich plasma or PRP. The name Priapus Shot® is registered with the US Patent & Trademark office as a “service mark” to protect patients by indicating a specific protocol. The name is not a synonym for the injection of blood in to the penis—such a definition would not be specific enough to warrant protection as intellectual property and so would not indicate any particular quality of care.

    The trademark gives a method of teaching a specific protocol that providers agree to follow and develop; this agreement offers a measure of quality control and is being followed and developed by around 500 urologists and interventional radiologists, family practitioners, and internists in multiple countries and by faculty in several medical schools where further studies are being done.

    The Priapus Shot® procedure defines a protocol that involves patient selection, patient evaluation & education (including explanation of consent), preparation of the PRP, local anesthesia, PRP injection, post injection use of a penis pump on a daily basis, and a daily dose of Tadalafil. Other post injection steps can include: stopping smoking, CoQ10 (12), vitamin E (13), Trimix, and aerobic exercise. Protocol steps can vary depending on the problems presented by the patient.

    It is the policy of most of our providers of the procedure to offer any patient that is not happy with the Priapus Shot® procedure a complete refund.

    Find Priapus Shot® Provider <–

    Patient selection includes identifying those who may need hormonal treatment, or family counseling, or vascular surgery, as well as those who may have co-morbidities or who may be taking drugs that interfere with sexual function. Some patients are not treated with the Priapus Shot® protocol because another treatment or no treatment is more appropriate.

    Consulting the patient includes informing him that unexpected side effects could occur and the results can vary with some patients seeing no benefit.

    The preparation of the PRP involves a device approved by the FDA for isolating PRP from whole blood for autologous use. Since blood is not a drug, it is not governed by the FDA. Multiple kits have gained FDA approval. Some of the approved kits include Regen, Magellan, TruPRP, Eclipse, Pure Spin, & Emcyte. There are over 8,000 papers on pub med discussing the science of PRP, and not one serious side effect has been documented when FDA approved kits were used to prepare the PRP.

    The first indication that PRP may be useful in the penis is in a paper published in Urology in 2003 indicating that, in animal models, using growth factors was successful to treat erectile dysfunction and indicated that such a strategy may be feasible in men— actually providing a way to correct underlying pathology (1). Viagra and Trimix do not correct underlying pathology of penile circulation.

    Another animal model study in 2010 showed that transferring adipocyte derived stem cells (ADSCs) into the penis caused endothelia cell growth as well as increased nitric oxide activity in the dorsal nerve. Interestingly, the ADSCs were tagged and perished – so the improvement seen was not from maturation of the ADSCs but rather from recruitment and activation by growth factors of stem cells from within the body. Also, indicating the PRP may demonstrate a similar effect (2).

    Dr. Virag (also a pioneer of Trimix injections) published a paper demonstrating improvement in erectile function, size, and correction of Peyronie’s disease with the use of PRP. His studies both published (and to be published) demonstrate a mean increase of 7 on the ED Intensity Score when PRP is injected into the plaque and the corpus cavernosum of the human penis (3).

    One of the growth factors (over 20 known) found in PRP includes vascular endothelial growth factor (VEGF). In one animal model study, the animals were castrated to create a penis that demonstrated, on microscopy, atrophy of smooth muscle and nerves as well as endothelial cell pathology. Injecting VEGF directly into the corpus cavernosum prevented the atrophy as effectively as did testosterone replacement. Moreover, VEGF reversed cavernosoetric findings of leakage (4).

    The above studies and others not cited indicate an improvement in the health, circulation, and strength (density) of penile tissue.

    In regards to improvement in erection firmness, the Priapus Shot® protocol also includes a recommendation of aerobic exercise which by metaanalysis of 5 randomized controlled studies using the IIEF showed an increase of 5 (5,6).

    As previously stated, the complete Priapus Shot® protocol, also includes the use of a penis pump, which as a stand-alone therapy has been demonstrated to improve erection both as part of a penile rehabilitation program as well as an adjunct to other therapies (7,8).

    This same penis pump strategy, even without the PRP, has been demonstrated to increase penis size by 2-3 cm, while traction (another physical therapy that can be included as part of the Priapus Shot® protocol) was shown to increase penis length by 1.5-2.5 cm (8, 9). Adding PRP to the protocol shows improved results according to data collected by urologists currently utilizing the Priapus Shot® protocol – to be presented later this year. It should be noted that the 2.5 cm improvement seen with the penis pump alone is in the 10-20% growth range for the average sized penis. As previously stated, while patient results vary, any patients that are not happy with the procedure are given a complete refund.

    Ultrasound studies of humans, post treatment, by Dr. Virag and by the physicians currently utilizing the Priapus Shot® protocol demonstrate improved blood flow and an increase in endothelium (improved health) as well as such results being indicated animal model studies, only some of which have been cited.

    Dr. Virag’s studies, using the injection of PRP as a stand-alone (without physical therapies), also demonstrate improvement in the angle of the penis in men suffering with Peyronie’s disease (3). Also, strict adherence to a penis pump regimen is part of the Priapus Shot® protocol and the pump alone improves the angle significantly in over one-half of those studied in one study in the British Journal of Urology (10). This same study demonstrated growth of the penis using the pump alone (without the PRP injection) though the growth was not as significant as in the other studies previously cited. The PRP alone, in Dr Virag’s study, out-performed the pump with demonstration of remodeling of the plaque.

    Studies show that the non-surgical treatment of Peyronie’s is most effective when a synergy of multiple modalities is engaged (11). So, the Priapus Shot® procedure includes the injection of PRP (demonstrated effective by Dr. Virag) combined with daily physical therapy using a penis pump for ten minutes twice a day and a daily low-dose of Taladafil. Further, other modalities are also used in the Priapus Shot® procedure that have been demonstrated to be synergistic: stopping smoking, CoQ10 (12), vitamin E (13), Trimix, and aerobic exercise. Such strategies are not intended to take the place of surgical correction or of the use of chemical surgery with collagenase—but rather to offer the man suffering with Peyronie’s disease the optimal non-surgical treatment as a first step with surgery reserved if non-surgical therapies fail.

    The Priapus Shot® protocol does not intend to make any particular therapy obsolete but rather offer a protocol for enhancing an overall, synergistic approach to pathology of the penis. The surgical treatment of Peyronie’s disease can be unsatisfying and lead to serious complications (14); we are seeing the safety profile of PRP and the Priapus Shot® protocol offer an appealing conservative step to take before proceeding to surgery.

    For, example the penis pump alone (part of the Priapus Shot® protocol) has been shown to improve the effectiveness of Cialis and of Trimix injections (8). We are seeing men decrease the dosage of Viagra and/or Trimix by about 50 percent when the complete Priapus Shot® protocol is used.

    Most men find the procedure very comfortable if a topical lidocaine cream is used since a 1/2 inch 30 gauge needle is used for injection (similar to a Trimix injection). However, some men do ask for a dorsal nerve block which can easily be done using 1% lidocaine without epinephrine for a near painless procedure (since this same block can be used for prosthesis placement, it makes a 30 gauge needle completely painless for most men) (15).

    Considering the duration of effectiveness and risks involved it’s useful to consider the nature of the cell biology employed. A review article considering the basic science discusses the fact that the autologous growth factors are exactly what’s generated to propagate healing should the man have surgery. The healing peptides, chemotactic factors, and pluripotent stem cells employed are exactly what’s generated by the normal healing process and offered no inherent risk for infection or allergy (16).

    In over 8,000 papers published about PRP on pub med, there is not one serious sequelae reported that I can identify (multiple review article speaks of the safety). This seems logical when you consider the material being injected is autologous and normally produced to help healing and to fight infection.

    Wound care studies demonstrate the nature of multiple tissue types being regenerated (with no reported risk of neoplasia in multiple biopsy studies (17-20).

    Moreover, in rat studies (where biopsy of the dorsal nerve is feasible), PRP has been shown to help regenerate nerve tissue and restore erectile function when prostate surgery is modeled with crush injury to the dorsal nerve (21,22). Some studies of stem cell therapies demonstrate that the stem cells do not actually mature into healthy tissue but rather signal for the improvement of the involved ganglion and nerve conduction by recruitment of stem cells to the area – exactly what happens with PRP.

    Stem cells are not directly prepared as part of the Priapus Shot® procedure, but we are seeing similar results as what’s reported with stem cell studies. Stem Cell studies often use PRP as a carrier for the stem cells, bringing into question which is the active agent (23-24).

    The idea of safety is further emphasized by the literature indicating that not only are there no reports of serious allergic reactions to PRP, but research also shows that PRP can attenuate the autoimmune response. One split-scalp study (with placebo control) showed improvement in alopecia areata, with the use of PRP, that out-performed triamcinolone (25). Another study using PRP in the genitalia of women, showed improvement in lichen sclerosus as determined by both patient survey and by 2 blinded dermatopathologists (26). This attribute of PRP, that of attenuation of the autoimmune response, could partly explain the effectiveness of the Priapus Shot® protocol for the treatment of both Peyronie’s disease and erectile dysfunction.

    In summary, multiple studies support the idea that blood-derived growth factors (when prepared in a proper way using a kit approved by the FDA for the preparation of PRP), as used in the Priapus Shot® protocol, support the health and function of the penis. Erectile dysfunction is associated with anhedonia, and successful treatment leads to better function, better relationships, and more pleasure in life (27).

    References

    1. Siroky M. Vasculogenic erectile dysfunction: newere therapeutic strategies. J Urol. 2003;170(2 Pt 2):S24-9.

    2. Garcia MM, Fandel TM, Lin G, Shindel AW, Banie L, LinC-S, and Lue TF. Treatment of erectile dysfunction in the obese type 2 diabetic ZDF rat with adipose tissue-derived stem cells. J Sex Med 2010;7:89–98

    3. Virag R. A New Treatment of Lapeyronie’s Disease by Local Injections of Plasma Rich Platelets (PRP) and Hyaluronic Acid. Preliminary Results. e-mémoires de l’Académie Nationale de Chirurgie. 2014;13(3):96-100.

    4. Rogers R. Intracavernosal vascular endothelial growth factor (VEGF) injection and adeno-associated virus-mediated VEGF gene therapy prevent and reverse venogenic erectile dysfunction in rats. International Journal of Impotence Research. 2003;15:S24-9.

    5. Lamina S, Agbanusi E, Nwacha RC. Effects of Aerobic Exercise in the Management of Erectile Dysfunction: A Meta Analysis Study on Randomized Controlled Trials. Ethiopian Journal of Health Sciences. 2011;21(3):195-201.

    6. Esposito K, Giugliano F, Di Palo C, et al. Effect of Lifestyle Changes on Erectile Dysfunction in Obese Men: A Randomized Controlled Trial. JAMA. 2004;291(24):2978-2984. doi:10.1001/jama.291.24.2978.

    7. Nikolai S. Erection rehabilitation following prostatectomy–current strategies and future directions. Nature Reviews Urology. 2016;13(.):216-225.

    8. Pahlajani G,Raina R, Jones S, Ali M, and Zippe C. Vacuum erection devices revisited: Its emerging role in the treatment of erectile dysfunction and early penile rehabilitation following prostate cancer therapy. J Sex Med 2012;9:1182–1189.

    9. Sellers T, Dineen M, Wilson SK. Vacuum protocol and cylinders that lengthen allow implantation of longer, inflatable prosthesis. Toronto, ON: (Abst) Society of Sexual Medicine; 2008.

    10. Raheem A. The role of vacuum pump therapy to mechanically straighten the penis in Peyronie’s disease. BJU Int.. 2016;117(4):E7.

    11. Levine L. Peyronie’s disease: contemporary review of non-surgical treatment. Transl. Androl. Urol. 2013;2(1):39-44.

    12. Safarinejad M. Safety and efficacy of coenzyme Q10 supplementation in early chronic Peyronie’s disease: a double-blind, placebo-controlled randomized study. International Journal of Impotence Research. 2010;22(5):298-309.

    13. Paulis G. Efficacy of vitamin E in the conservative treatment of Peyronie’s disease: legend or reality? A controlled study of 70 cases. Andrology. 2013;1(1):120-128.

    14. Lue T. The Challenges of Peyronie’s disease. Translational Andrology & Urology. 2012;1(S1):PS 9.

    15. Raynor M. Dorsal Penile Nerve Block Prior to Inflatable Penile Prosthesis Placement: A Randomized, Placebo‐Controlled Trial. The Journal of Sexual Medicine. 2012;9(11):2975-2979.

    16. Sanchez-Gonzales J. Platelet-Rich Plasma Peptides: Key for Regeneration. International Journal of Peptides. 2012;10:1-10.

    17. Taylor D. A systematic review of the use of platelet-rich plasma in sports medicine as a new treatment for tendon and ligament injuries.. Clin J Sport Med. 2011;21(4):344-52.

    18. Yuan T, Zhang C-Q, Wang JH-C. Augmenting tendon and ligament repair with platelet-rich plasma (PRP). Muscles, Ligaments and Tendons Journal. 2013;3(3):139-149.

    19. Sell S. A case report on the use of sustained release platelet-rich plasma for the treatment of chronic pressure ulcers. The Journal of Spinal Cord Medicine. 2011;34(1):122-7.

    20. Conde-Montero, E., Horcajada-Reales, C., Clavo, P., Delgado-Sillero, I. and Suárez-Fernández, R. (2014), Neuropathic ulcers in leprosy treated with intralesional platelet-rich plasma. Int Wound J. doi:10.1111/iwj.12359

    21. Ding X. The effect of platelet-rich plasma on cavernous nerve regeneration in a rat model.. Asian J Androl. 2009;11(2):215-21.

    22. Ding X. Platelet-rich plasma on the Cavernous Nerve Regeneration. Chinese Medical journal. 2008;88(36):2578-2580.

    23. Rene’ Y. Safety of Intracavernous Bone Marrow-Mononuclear Cells for Postradical Prostatectomy Erectile Dysfunction: An Open Dose-Escalation Pilot Study. European Urology. 2016;69(6):988-991.

    24. Fandel T. Recruitment of Intracavernously Injected Adipose-Derived Stem Cells to the Major Pelvic Ganglion Improves Erectile Function in a Rat Model of Cavernous Nerve Injury. European Urology. 2012;61(1):201-210.

    25. Singh S. Role of platelet-rich plasma in chronic alopecia areata: Our centre experience.. Indian Journal of Plastic Surgery. 2015;48(1):57-9.

    26. Goldstein A. ISSVD 2015 Abstracts. Autologous Platelet Rich Plasma (PRP) Intradermal Injections for the Treatment of Vulvar Lichen Sclerosus. Journal of Lower Genital Tract Disease. 2015;19(3):S1-S25.

    27. Goldstein A., Runels C. Intradermal Injection of autologous platelet-rich plasma for the treatment of vulvar Lichen sclerosus. Journal of the American Academy of Dermatology. 2017;76(1):158-160

    27. Zaman H. Association of psychological factors, patients’ knowledge, and management among patients with erectile dysfunction. Patient Preference and Adherence. 2016;10:807.

  • Peyronie’s & ED Treatment…”Supplements & Foods that Cause a Harder Straighter Erection”…


    (scroll down to read transcript of this video)

    Priapus Shot Providers (click) <–

    Resources & References (Video Explains)…

      • Pycnogenol

             Viva Naturals Pycnogenol 100 mg on Amazon


    • Double blind study of Co-Q10 (click to read)<–
      • 186 men with “early chronic” Peyronie’s got 300mg Co-Q10 per day. The other group got placebo.
      • No other treatment!
      • At the end of 6 months…
        • Placebo group-average plaque size and curvature increased. 56% of the men in the group were worse. No one was better.
        • In the men who took 300mg Co-Q10, average plaque size and curvature improved and erectile function improved! Only 13.6% of the men worsened.
      • Conclusion. Co-Q10 prevents worsening 87% of the time, and improves curvature & erectile function & decreases plaque size in most men after 6 months of treatment.
      • Recommended Co-Q10. This is a 6 month supply of high quality in 1 bottle. Put this buy where ever you have your morning meal or protein shake and take with that….

         CoQ10 400 mg capsules on Amazon


    • Vitamin E used in combination with other therapies. (Click to read)<–
      • Men with Peyronie’s were divided into 2 groups and treated for 6 months.
        • In 1/2 of the men, vitamin E  at a does of 1,200 IU was give once a day as part of a combination therapy.
        • The other 1/2 got the combination therapy without the vitamin E
      • The men who did not get the vitamin E saw and average decrease in curvature of 6 degrees. Average reduction in plaque was 36%. Of the men treated, 48% improved.
      • With the men who DID get vitamin E, an average decrease in curvature of twice as much occurred–12%. The average plaque reduction was 50% and of the men treated 96% improved!
      • No one in the vitamin E group saw a worsening of the curvature or an increase in the size of the plaque. Some of the men who did not take vitamin E did see an worsening of the curvature with 17% of them seeing an increase in the size of the plaque!
      • The vitamin E group also saw a more significant increase in erectile function.
      • This is a wonderful example of the “fire” analogy. Sometimes it takes more than  1 thing a the same time to build a fire.
      • One of each of these per day gives 1,250 IU’s (1,000 + 250) with an excellent quality and a few cofactors that help the E work better…

      <–one of these + one of these–>

    Beginning of Transcript of Webinar…

    Save

    Save

    Save

    Save

    Save

    Save

    Save

    Save

    Save

    Save

    Save

    Save

    Save

    Save

    Save

    Save

    Save

    Save

    Save

    Save

    Save

    Save

    Save

    Dr Runels: So thank you guys for coming. There’s this idea by some people that whatever you have with your erection, you can only make things better by taking medicines, and that the blood flow through the penis itself can’t be improved, but as a matter of fact it can be improved, and there’s research dating back at least the past 15, 20 years demonstrating that that is possible. Before, there was a Priapus Shot®.

    So as we go through this, I’ll just run through this and lay down the research the best I understand it. There may be some other physicians on the phone here, actually I see several other physicians on the phone, and so at some point I’ll open the floor for discussion and I’ll also open the phone of some of the other physicians so that we can answer your questions.

    After spending years, 25 plus years taking care of people, and intensively studying for the past few years ways to make the erection better specifically, other than things … if you think about it, if you take Viagra, that’s a great drug, but it’s not doing anything to correct the problem, it’s just making what’s there work harder. Same with an implant, but the idea of actually making the blood flow itself into the penis better is what we’re talking about here.

    Some of you may be on this call because you subscribe to this newsletter here where I intend to put down what I determined from the medical literature to be things that have been proven to be helpful, like hormones, exercise, of course our priapus shot, nutrition, using a pump, so today’s topic is about the pump, and we’ll go to the sort of an outline, and I haven’t made this page available yet, but here are some of the most powerful things I’ve seen, and a lot of this, this comes from a lot of research, but much of what I’ll show you is summarized in a paper that you’ll find a link to on the page right here, and when you click on that it takes you there. I’ll tell you how to get to this page after the webinar, and I’ll post a recording of this right there at the top of the page so you can review it.

    If you click on that, it takes you to this excellent review article that goes into all the things that have been demonstrated in the way of lifestyle and eating and supplements to improve the erection and how that works. So the most powerful one is exercise. I hate to say it, some people hate exercise, but so important that I’ll cover that in a separate webinar.

    But getting to the supplements, folic acid, antioxidants, calcium I think is less helpful, vitamin C, vitamin E, and again hormones will be covered in another episode. Now when it comes to the antioxidants what I’ve observed and others, and what the research shows is that C and E are helpful, and even for Peyronie’s disease there’s a double-blind, placebo controlled study that I’ve posted, showing that, if you go to this part here about vitamin E and click on this, there was a double-blind … this showed that using the vitamin E helped Peyronie’s disease.

    Also there was a study here with CoQ10 where they took 196 men with early chronic Peyronie’s and gave them 300 mg of CoQ10 per day, and no other treatment, and then at the end of the six months, the people who were taking the placebo on average saw a worsening, and no one was improved, but in the people who took the coq10, the plaque size improved on average and only 13 percent of them worsened. This was a true placebo controlled study.

    All of the studies show that there’s a synergy, there’s an actual synergy, so what I see, and this is a huge problem I think, is that people will try one thing and they think that doesn’t work, so they discard it instead of adding that one thing to the other things. My favorite analogy with that is starting a fire. If someone told you, and you had no idea what a fire is, told you to light a match, you wouldn’t see very much, so you decided okay, matches don’t work. And the next day someone told you that you should use wood, pile up a bunch of wood, but alone of course that wouldn’t do much for a fire. Someone says, okay really what you need to make a fire is a stack of wood, put some lighter fluid on it, and then light a match, then you would have a real fire.

    This is what you’re looking at, this picture is the match that starts the erection fire of improved erectile function in your penis. The way this works is that nitric oxide, neuronal nitric oxide synthase relaxes the arteries, so the things that promote neuronal nitric oxide are these, and you have to have the right dose, at least enough of the stuff.

    Vitamin C I like at least three grams a day with food, vitamin E at least 1250 mg, that’s what’s in the research. Now, let’s go and look at arginine and citrulline, because that’s very interesting, if you look at what he writes about here, he said there was no effect at all at the lower dose of one and a half grams per day. That’s a big tablet, most people have trouble swallowing a tablet that’s more than one gram. But in a randomized trial of five grams per day, there was improvement in 31% of the men.

    What I recommend is arginine or glutamine at four grams, three times a day, twelve grams a day. If you take that in tablets it gets to be very expensive, so what I recommend you do is buy it in a powder and taking that many pills will exhaust you, so I recommend that you mix the powder with water. Now, hang with me here, because it does no good in my opinion to look at all this research. As a matter of fact, I don’t like looking at research unless there’s a way to actually use it to make people healthier.

    I like the science piece of it, sometimes it’s interesting, but if I can’t tell you exactly what to do to make your life better and your erections better, then it’s a waste, you might as well be watching the news. So I’m telling you how to implement this. Everything on here is going to be exactly how to do it.

    So arginine. Not only does arginine help with nitric oxide production, but what he doesn’t say right here is arginine and glutamine both, taken on an empty stomach, stimulate the pituitary gland to release growth hormone, which causes somatomedin C production by the liver and other tissues. So it causes you to make more growth hormone, which also is associated with firmness of erection and associated with decreased vascular disease. It’s a cheap way of taking growth hormone, but it doesn’t work if you mix it with your milkshake or your food because it doesn’t act pharmacologically.

    So for it to have its effect on the pituitary gland, arginine or glutamine or citrulline, they have to be the only amino acids in the bloodstream. A practical way of doing this is to wake up, and the first thing you take in the morning is not food, and it’s not your protein shake, it’s the things that work best on an empty stomach. So that might be your SAMe, if you take SAMe, it’s your arginine, if you’re taking thyroid medication, this is when you take your thyroid with something without amino acids like water or some juice.

    Then you wait about 20 minutes, you don’t have to wait a long time, 20 minutes before you have your protein meal, or protein shake, or whatever you’re doing. So arginine, they say three grams once a day, I would say that’s a minimum. Shoot for four grams three times a day on an empty stomach. Now how to get an empty stomach three times a day. What you do is when you think of eating, take the arginine first, just mix a scoop of it. It’s interesting, in the pills, hard to get it down, it’s a bunch of pills, but you’ll see four grams in a scoop is not very much. Mix it in half a glass of water or juice or something, you down it, and wait 10 or 15 minutes before we eat. Arginine is huge.

    Now, testosterone. We’ll get to, when we talk about hormones in a future episode, it’s huge but it’s not the subject of today. Omega 3 fatty acids, you’ll see here he talks about that, it’s proven over and over again it helps circulation. They recommend a gram of omega 3 fatty acids because that’s what the American Heart Association talks about.

    I’m not as big a fan of folic acid. You can read the paper, take it if you want. Calcium I think it makes people constipated sometimes, and although talk about lowering blood pressure, I think magnesium lowers blood pressure better than calcium, so I’m not as big a fan of those. Vitamin C they say 500 to 1000 mg. I would reduce that to 300 mg, but take your vitamin C at the beginning of a meal, so don’t take it with an empty stomach because it’s acidic, take your vitamin C and your vitamin E at the beginning of a meal.

    So let’s go back and look at this again. So arginine and citrulline, arginine’s what I would go for. They are going to help with the nitric oxide, promote it, and they also boost growth hormone levels, which he doesn’t talk about here. He also mentions another antioxidant that I put here on the page, this. Pycnogenol, it’s a very, very, very powerful antioxidant, but you need to take it at least 100 mg per day, and you can take that with food.

    Now, what about food? It’s interesting to me, by the way this whole, remember you can click there to get to this article and I’ll give you a link to this shortly. Food. Food is, it’s interesting to me when people talk about, we want to talk about medicines and supplements, which are measured in milligrams. Think about this for a second. Your food is measured in pounds. So if milligrams of supplements can have an effect on your body and your life and your brain and your sexual function, you better believe that food can make a huge, huge difference in your life, and your body, and the way you feel.

    Now, I did some research participating with Dr. Atkins. I went to San Francisco when Barry Sears first came out with his own diet. Actually their zone bars, you have to be a certified provider, and be in his training, which was more nutrition by far than I ever learned in medical school, before you could sell the zone bars. I never sold the zone bars when I went out and trained with him, and I’ve come up with my own ways of combining things.

    The problem with the Zone diet is that it’s difficult, it takes a lot of time. The low carb diets are not so energizing, so it gets confusing when people talk about food. Counting calories, people don’t like that. The bottom line is, after taking care of people for 25 plus years, and I ran a weight loss clinic for about 12 of those years, it’s just miserable when people start trying to monitor their food. So there are some principles that I like to teach, and I would recommend two things. I would recommend the Zone book sort of as a way of swinging two bats before you swing one. If you just make a point, and his website’s very supportive, make a point of following his diet the best you can for about a week, you’ll learn some principles.

    For example, it’s best to eat about the number of calories that you’ll need over the next three hours or so, and then you’re sort of titrating the amount of calories, and then if you get the ratios right of protein, carbohydrates, and fat, there’s neither a lethargy nor a hunger, both of which make you not at your best function, which is the idea behind the Zone, like a zone an athlete is in.

    Now, trying to come up with a cram course in how to teach you both the ideas of fasting, which also does some things with growth hormone, it does some things with your pituitary gland and your brain that make sex better, not during the fast but immediately afterwards, and how to teach the zone, and how to teach low carb, I came up with this crash course that I call the three day fat burn, and it comes with some ideas about exercise. Either way, get one or both of those if you need to think about your nutrition, because if you go back to this article, it is absolutely imperative, if you look at this, look at food. What inhibits, doesn’t matter if you’re doing your testosterone, your vitamin E and your vitamin C, it does not matter.

    You realize this inhibits, so this is lighter fluid for your erection fire, this is water. All these things are putting water on your erections. Smoking, I think if you’re a smoker you probably should just consider being a priest, because eventually most guys who smoke, not all, but most guys eventually have some problems with their erections if they’re smoking. I don’t want to start preaching about smoking. I have some ideas, I have a very high success rate with addiction in general in my practice, and I’ll tell you right now, the smoking idea, I’ll give you a preview because I have an episode of this coming up, here’s a preview.

    Freud says you never quit a habit, you only substituted one for the other, but if it’s a strong habit like smoking, you have to substitute a bunch of habits for the one habit of smoking, and so I cover that later. High fat, high sugar intake, I think the sugar is by far, in this article you see is 17 years old, but it’s still very, very true, and the parts that aren’t true I’m telling you, and the high fat has become less important than it was 17 years ago. Now we know you can actually lower cholesterol, and lower and improve blood pressure with high fat diets, as long as they’re low sugar.

    If you’re high fat and high sugar you’re just going to gain weight and it’s poison. Sugar is the thing that’s the poison, and when people say they go on diets where all they do is cut out sugar and white bread, well white bread, bagels, that’s just sugar in disguise. It almost instantly turns into sugar, so you might as well just take a spoonful as sugar any time you eat white bread or pizza crust or a bagel. It’s literally like eating a candy bar.

    The obesity of course, and diabetes, we’re not talking about the results here, I’m talking with you about the habits of food, and supplements that will change these other things. Of course diabetes and obesity, because diabetes interfere with erections, because diabetes causes nerve damage, it causes increase atherosclerosis. This is key, and a lot of patients, a lot of people don’t think about this. I want you to think about this really, really hard if you’re a diabetic person, if you’re a person suffering with diabetes, or the trouble of having diabetes. Lowering your blood pressure tied to diabetes, not type I, if you’re a type II adult onset, which now sometimes occurs in children, if you suffer with type II diabetes, lowering your blood sugar with a drug is like force feeding your body.

    Realize the reason the high blood sugar occurs is your body says, “I’ve got enough nutrition here.” The insulin receptors go down, so the insulin doesn’t work anymore, so insulin levels go high. That’s why it’s called insulin resistance. And blood sugar goes up because the body says, “I don’t want this sugar anymore, i already have all the sugar I need.”

    So it goes high in your bloodstream and you start to urinate the sugar, you start urinating a lot. Now, when you take the insulin, or you take the drug, you’re basically force-feeding the body that extra sugar instead of just not eating, or going for a walk and burning the sugar off. The reason I tell you all that is, if you suffer with diabetes I want you to know that, just like being on a blood pressure pill and controlling your blood pressure does not take away the risk of hypertension for increasing your risk of heart disease, having the diagnosis of diabetes and insulin resistance does not take away your risk or problems from that.

    As a matter of fact, the research shows that the more tightly you control your blood sugar, more than one study, both as an outpatient and in the hospital, the more tight you control your blood sugar, the more you have an increase in heart disease and stroke. That’s a really scary thing, because you’re stuck. You need to take the medicines to keep from the problems of hyperglycemia, but yet if you take the medicines then you have problems, too, and that’s why, because it’s basically force-feeding.

    The way to deal with it is increase insulin resistance, and decrease diet at the same time. Increase resistance by exercise, and to do that, if you’re on medicines you really need the supervision of a doctor. I don’t want to dwell on that too much, but there may be some people dealing with diabetes right now and you need, in my opinion, I hate to say it but unfortunately the nutritionists who were trained by the powers that be that deal with diabetes, in my opinion, often they’re not as effective as something, a combination of therapies using something like the zone diet with walking.

    The walking or the exercise, again we’ll get to that later, but it’s not 30 minutes two or three times a week, it’s just not adequate. But I have a way of making it easy, so we’ll get to that.

    Back to his list, he’s got … I think we’ve covered, and then I have a couple more we’ll talk about. So the inhibitors are high fat, although the fat doesn’t bother me much, the poisonous sugar, smoking, excessive alcohol. The alcohol changes, here’s the thing about alcohol, it changes the way you metabolize sugar. It’s not just the sugar in the alcohol, and that’s where some of the commercials sort of trick them. They do trick people, because having a low calorie alcoholic drink doesn’t make it not change they way you’re dealing with sugar. It’s effect on the liver has an effect on the way you metabolize sugar that makes you more susceptible to problems with metabolism, even if alcohol itself doesn’t have that many calories in it.

    Again, I’m not trying to turn you into a priest, but my advice to people is instead of doing drugs like alcohol and caffeine, be a drug. That’s what one of the gurus said. Be a personality that is a drug instead of taking drugs.

    Again, I don’t want to preach at you too much, I’m just telling you we’ll get to this later. As a matter of fact, I don’t even want you to try to quit the stuff now, I just want you to focus on the things to do, and the things to do we’re talking about so far are the arginine, the vitamin E, the not so much calcium, the antioxidants, vitamin C, and folic acid. Now, this nitric oxide promotes cyclic GMP, which causes the erection. The reason Viagra, which is PDE5, the reason it helps the erection is it inhibits the breakdown of the cyclic GMP.

    Let’s go back to here, we’re getting close, there’s no reason to make this go, I’m going to open the floor to questions here in a minute. Let’s go back to our thing here. So coq10, vitamin E, we talked about, when it came up here … by the way you can click on these and order from Amazon. You might have another source, but I just shopped Amazon for the best price on what I thought was the best quality. This is 1000 mg and 250 mg, that includes some other things that help.

    Okay, so we’re into this long enough I think I’ll stop here and open it for questions. Before I do, I want to show you, this will be the second in this lesson. We’ve talked about pumps already. We’ll talk about the priapus shot in the next one and really details about hormones and exercise, and then my tips on how to quit smoking. If you want to get the whole thing and you’re not subscribed, here’s where to subscribe. It’s priapusshot.com/peyronies. Even though I’m talking about Peyronie’s and researched that literature very carefully, everything I’m talking about here helps erections as well.

    Before I open it to everybody, let me see, is there any physicians on the phone who want to add to what we’ve talked about so far, just raise your hand and I’ll unmute your mic, because I know there are some people. Then I’ll unmute the mic for anyone else who has questions. So let’s see. Elizabeth Owings. So let me unmute your mic, Elizabeth. So Dr. Owings, let me give you a little preview. Dr. Owings has an amazing resume, she’s been trained as a pediatrician, a pediatric surgeon, four different residencies, just a brilliant woman, and she’s one of our priapus shot providers and she’s had some experience that I think she wants to share. Let me see if I can unmute you.

    Elizabeth? Dr. Owings?

    Elizabeth Owings, MD: Yeah, can you hear me?

    Charles Runels, MD: Beautiful, yep. You’re up.

    Elizabeth Owings, MD: Can you hear me?

    Charles Runels, MD: Yes. Can perfectly.

    Elizabeth Owings, MD: Okay great. All right, I just wanted to give some hope because I’ve not worked with a lot of men with Peyronie’s disease, but I’ve worked with a lot of men with erectile dysfunction. I was the chief medical advisor of a supplement manufacturing company for many years, so I know my way around the herbal and nutritional world, the amino acids, the arginine and citrulline. We saw some incredible results with combination products, especially arginine plus citrulline, these two things together. Apparently arginine can be turned interesting nitric oxide, or it can be turned into urea.

    One of the things that citrulline does is drive it towards that nitric oxide pathway, and it’s just a beautiful thing when you see that work. Just a little piece of hope, I’ve seen men, diabetic, no erection for 20 years. I’m sorry, someone’s trying to call in. No erection for 20 years, successfully complete intercourse after three to six months of combination products like this. That just brings hope because you know that this, it’s like this relationship is flowering all over again.

    That’s the main thing I wanted to share. Blood pressure tends to get better, all sorts of things get better when you’re supplementing these things.

    Charles Runels, MD: So what does … two things, first of all three to six months, this is not … a lot of people think food and nutritional things can be immediate, usually they’re not, as she just pointed out. Usually with the change in metabolism there’s a change in body, and I know when you change someone’s hormones it takes four years for the full effect to take. For example, a woman has a hysterectomy, it’s usually three to four years before … and she’s not properly hormonally replaced, so you remove her ovaries, her hormones go crazy. It’s usually weight gain for three to four years before she levels off.

    Same thing if a man starts taking testosterone, lifting weights, his body will change and he’ll plateau three to four years out, so even three to six months is really fast for a metabolic change where you’re rebuilding tissue. Obviously these are causing, rebuilding also is causing an accumulation of this nitric oxide, neurotransmitters, nerve. So I heard three to six months. Tell us what dosages you were using when you were in this experience.

    Elizabeth Owings, MD: In that particular experience, it was going to be arginine at five to ten grams a day, and this was a liquid product we were working with, although I’ve had equal results with a powder, this particular one was liquid. I think I’m happier with the powder, we had a lot of diarrhea with the liquid, something about one of the mineral masks or something, but that’s okay.

    Plus 200 mg of citrulline, 2-400 mg of citrulline. Now, I have seen a product that had some remarkable blood pressure results clinically in a study, that used 1000 mg of citrulline. It was a combination product. Again, just like you said, one of the frustrating things about some of these articles is that they’re trying to do one thing at a time, and that’s the way you’re supposed to do it in your test kitchen, but when we’re trying to get someone better from a disease they’re not supposed to be able to get better from, I say throw everything at it, do everything. Why are you holding back?

    Charles Runels, MD: Yes.

    Elizabeth Owings, MD: You have to do your studies in a certain way, but when you’re trying to help people get better like we are, I say give the body every chance that it needs, because you don’t necessarily know what tests to order to find out what they’re deficient in sometimes. You just know that if we do this combination of things they’re going to get better.

    Anyway, most recent one had I think a gram and a half of arginine and a gram of citruline, and some other things like a micronized cayenne. They didn’t have hawthorn in this one, but just a couple other things in there, red yeast rice extract. Several things put together and you’re really going to see good results with that.

    There are lots of things out there. You can get a good testimonial from anybody, I’m just saying there’s hope. If you’ve been told there’s no hope, and you’ve been impotent for 10 or 20 years and you just live with it, I’m telling you there’s hope.

    Charles Runels, MD: Beautiful. Let’s see, so stay on the line. We may have someone else that you can help me with. Someone wrote in and said, “I’ve noticed I have back pain from taking one to two grams of arginine. Do I just need more water?”

    I’ve heard the diarrhea and nausea. Glutamine has a similar effect of arginine, so that’s an idea, but you have any ideas on that, Dr. Owings, as far as the back pain? That’s a new one for me.

    Elizabeth Owings: I don’t think I’ve run into that before, although I’ll tell you where the conversion is, is in the liver and the kidneys. I don’t know, it may be one of those things where you want to spread the dose out and see if the back pain goes away. I’m not as strict a disciplinarian as I used to be, nothing happens twice a day, or heaven forbid three times a day in my house. I have to take my arginine first thing in the morning or the last thing before I go to bed. Two scoops go in my big bottle of water, I shake it up and down it while I’m doing my workout or whatever.

    This may be a person that wants, instead of that approach, spread it out two or three times a day and see if that doesn’t improve it. I wish I knew where the back pain was, if it was central or bilateral, or …

    Charles Runels MD: I’ll go along with what you said earlier, too, about powder versus liquid. I just think the powder’s easier to carry around obviously than the liquid, as far as the practicality of taking something two or three times a day. The only way I’ve found to do that is to keep it at home, wherever I eat breakfast, and at the office or in my backpack when I was an ER doctor, so that whenever I ate lunch it would be there and it would be the thing I did right before I ate the lunch.

    But you’re right, unless you have something to trigger it, or it’s there with you all the time, then it’s almost impossible to do something three or four times a day. Let’s see if I see any other hands up. Let’s see.

    Annette has her hand up, we’ll see if I can … can you type the question in, Annette? I’m trying to unmute you.

    Someone is asking, would you give her a combination of items again, Dr. Owings?

    Elizabeth Owings, MD: Yeah, sure.

    Charles Runels, MD: So your ultimate combination.

    Elizabeth Owings, MD: Would include arginine, citrulline for sure, a combination of antioxidants, especially the ones that you cannot store, so your B and C, your B combination and C, vitamin D, it’s been shown to be a shepherd of the gene pool, we only have 20,000 genes, and vitamin D may influence up to 10% of those, and it appears to be favorable in every case. Down regulate cancer genes, and up regulate heart health things.

    I once downloaded a cardiology article that had like 150 references of the impact of vitamin D on the cardiovascular system and cardiovascular health and heart disease. So definitely at least 2000 IUs of vitamin D and 5000 is perfectly okay. There’s never been a toxicity associated with even taking 10,000 units of vitamin D a day. Don’t let them scare you.

    Those are going to be the main things. I love coq10, and now it’s less expensive. I’m not committed to whether the water soluble or fat soluble is better. I think it just depends. People have had their gallbladders out, there’s all sorts of factors that may play in there that are hard to determine, so I think the jury’s out on that one.

    I’m still a hawthorn fan, it doesn’t take a lot of the hawthorn berry to get some benefit. Red yeast rice, I mean they’ll still hold the shipment offshore for a little while because somebody’s trying to say it’s a drug because it’s the same active ingredient that’s in some of your statin medications. The reason your statins are dangerous is that they don’t have coq10. They knew that statins cause liver and muscle damage 20 years ago, and they thought about putting coq10 with it because it seemed to prevent that, and they just decided not to. I guess it was an expense.

    So definitely if you’re going to take the statin or you’re going to take something with red yeast rice, you better make sure you got your coq10. Probably even 30 mg is enough to offset some of the badness of it, but like you said up to 300 mg if you want the most positive effect.

    That’s a long list. I don’t know if any one product has all of those things, but those are the kind of things that I look at when I’m looking at a cardiovascular product.

    Charles Runels, MD: Let me add to some of the things you said. The vitamin D is not in this article, because as you know some of that research is more recent, and I just want to second that. Somewhere around 10,000 per day. The other thing that’s not really talked about very much anymore, there used to be a prescription version of yohimbe. It’s really hard to come by a pharmaceutical grade yohimbe, and if you don’t take the right amount, if it’s sort of low grade, it can make you have chills and headaches. But a 5 mg yohimbe, a pharmaceutical grade, would cure erectile dysfunction in 25% of men, and it’s one of the only things, only supplements out there that actually increases libido.

    Now, I can also make people irritable, and there’s talk about it can raise blood pressure, but if you do the other things that we talk about with the walking, I never saw the blood pressure problem, but if you use yohimbe you have to think about blood pressure headaches and irritability. But a pharmaceutical grade yohimbe will treat, before we had Viagra that’s what we had, and 25% of men with erectile dysfunction would be cured.

    Coleus root is another one. In rat studies, they castrated rats. C-O-L-E-U-S. They castrated rats and gave them, one group got testosterone, the other group got coleus, and coleus root caused them to start to have sex again as much as the testosterone. Let me add one other thing that I thought was interesting in this article, that the men who took a combination of arginine and pycnogenol also increased their semen volume, which you know some guys want to do that just sort of as a party trick sort of thing, it’s just fun to have lots of semen volume, but I think the semen volume contributes to libido, just like when you need to empty your bladder when it’s full, when your prostate’s full of fluid, of course that’s where most of the volume comes from is the prostate gland, when it’s full of fluid there’s I think more urge to have sex. I think that’s part of the reason our O-Shot® works is it causes women to collect fluid in their Skene’s glands.

    Let me see I we have any more questions. I think that’s … here we go. I guess that’s maybe it. We have other doctors on the call. Dr. Posey’s one of our doctors, and others here. Anybody else have anything they want to say? If not I’ll just shut it down, no reason to make it go on, but that’s sort of our secret formula, and sometime in the next week or so we’ll cover the next part of this idea, and we’ll talk more about the priapus shot, then hormones, and then my ideas about walking and things such as that.

    I’ll put this recording, I’m typing in here where it will be, it will be at priapusshot.com/food. So that’s where it will be, by in the morning we’ll have the recording there. I was honored you guys came and I hope you find this helpful. Thank you very much.

    Save

    Save

    Save

    Save

    What is the Priapus Shot® (P-Shot®)?
    See the research on the P-Shot®

  • Penis Pumps & How They Help ED & Peyronies…


    Priapus Shot® Providers

    Priapus Shot® Reviews

    Provider Application (Physicians & Physician Extenders)

    Edited Transcript of the above Podcast about Penis Pumps…

    Penis Pump
    Penis Pump Theory

    An erection can be modeled (in a physics way) as a water balloon. A balloon grows to a size to where the inside pressure equals the outside pressure. A balloon with no air pressure collapses because there’s no pressure on the inside to make it expand the balloon to match atmospheric pressure so the ballon collapses. When you blow into the balloon, then the balloon expands to a place to where the inside pressure matches the outside atmospheric pressure. Then it stops expanding.

    Diagram of the forces affected by a penis pump
    The Forces Affected by Penis Pump

    There’s another pressure that affects the balloon size that’s not immediately obvious—the tension or elasticity of the wall of the balloon. When you blow up a balloon, you can feel that tension and that it limits the size of the balloon and can feel that it’s the tension in the wall that makes it difficult to blow up the ballon.

    What can you do make it easier to blow up a balloon?

    Anyone who’s ever blown up a balloon for a kid’s birthday party knows that by stretching the balloon a few times, then when you blow into it the balloon is easier to expand.

    So, in regards to the penis, pressure provided by blood flowing into the penis (with venous return back to the heart being impeded so that there’s a one way valve) supplies the pressure that inflates the penis inflates. In addition, even though the penis is filled with tissue and not air, connective tissue, skin, & collagen all resist expansion, so that tension limits how big the penis can grow in the same way that the tension of the wall of a balloon limits it’s expansion.

    So, the size of ballon will be determined by where intra-penile arterial pressure equals the sum of the atmospheric pressure plus the tensile pressure of the penile tissue.

    Two forces contract the penis… (1) atmospheric pressure and (2) tension on the wall of the penis. One force expands the penis—the blood pressure within the penis.

    This blood pressure will be increased by increased arterial pressure and decreased by a venous leak. In this course, we’ll describe multiple ways to do these two things. You can’t do much about atmospheric pressure and that pressure contributes very little to the pressure forces on the penis, so the only other way legitimate way to decrease the forces that contract the penis is to decrease the penile tissue tension (PTT).

    Four Reasons for Using a Penis Pump

    There’s four reasons for using the pump: (1)you raise penile oxygen levels, (2)you avoid contraction, (3) you can stretch out the bent places and (4) you can get an erection with it.

    Always Stretch a Balloon Before Blowing it Up

    Studies show that a pump or a traction device will both decrease that tension including the increased tension in scarred areas that cause Peyronie’s, therefore allowing the penis to become straighter, harder, & sometimes larger. So, a pump is now accepted as part of the protocol for rehabilitating the penis post prostate surgery, improving erection quality and for treating Peyronie’s Disease.

    Stretch the Tight Places

    One study published in the British Journal of Neurology showed that when men who had Peyronie’s disease sufficient to cause curvature of the penis for which they wanted surgery were put on a pumping protocol, 51% of them canceled the surgery because they were pleased with the results after only 12 weeks of pumping. Along with that improvement, there was an increase in the size of the penis.

    Is Your Penis Holding It’s Breath?

    The flaccid penis is starving for oxygen. Not so much as when you put a tourniquet around your finger and it turns blue. Obviously, your penis doesn’t become necrotic just sitting around the house, but the flaccid penis has lower oxygen saturation that other parts of the body. So, the health of the penis partly depends on occasional erections which feed more oxygen to the penis. This is one of the reason for nocturnal erections, because that extra blood feeds oxygen to the penis.

    This penile oxygen saturation can be measured.

    When I managed a wound care center at a hospital, we had a hyperbaric chamber that would force extremely high levels of oxygen into the bloodstream (so much oxygen that a person could live without red blood cells from just the oxygen in the plasma). We used this method to help save the feet and legs of people with diabetes and poor circulation who suffered with ulcers—forcing oxygen-filled blood into the tissue to help heal wounds. Often, the circulation can be so poor that even hyperbaric oxygen does not help because there’s not enough blood flow. One of the ways you can figure out if the hyperbaric oxygen will help is by applying a stick-on sensor to the skin (similar to what you might see if you had an EKG) except that instead of measuring electrical current, it measures oxygen levels at the skin. It’s called trans-cutaneous oxygen saturation. Using that we would decide where we could save the leg and, if the person needed an amputation, where the surgeon might amputate so that he saves as much of the leg as possible but takes off the part where blood flow is inadequate.

    Back to penises…that same instrument can be used to measure the oxygen on the skin of the penis and then extrapolating get an idea about blood flow and oxygen levels inside the penis—penile trans-cutaneous oxygen levels (PTCO). Research showed that men who use a penis pump daily feed their penis oxygen. Even during other parts of the day (when they’re not using the pump), the their PTCO goes up!

    Researchers showed that Cialis works better if the man uses a penis pump. The improvement with the Cialis (the man can go down on the dose) might be from both the better oxygen flow and by stretching out the tissue so that the expansion needs less force due to less PTT.

    Pump Makes Erection

    Another benefit from the pump is the erection from the pump! A pump achieves an erection even without arousal and even in men who are not able to have an erection at all due to severe vascular disease or due to spinal cord injury. Before we had Viagra, a pump was an old-fashioned way of achieving erection in men who had suffered from severe vascular and erectile dysfunction. You put the vacuum pump onto the penis and then apply vacuum. When the penis is inflated with blood, a constrictor band is placed at the base of the penis, and that is enough tumescence enjoy penetration and sexual relations with a spouse.

    Now, hopefully you can, with this course, avoid having to use the pump to achieve the erection. Some people think they are going to damage their penis by using a pump, so I tell you about past uses of the pump so you know that like many therapies whether it’s beneficial or damaging depends on the intelligence of how the therapy is used.

    You can lift weights and achieve strength, or you can lift weights too frequently or with too much weight and cause injury. The same thing applies to the pump.

    Reasons you would not use a penis pump

    We just mentioned you could have too much pressure and damage the penis, and we’ll talk about how to avoid that later. Here’s the things that you may not be able to avoid: skin darkening, swelling, pain,

    Darker Penis

    One thing that often occurs is that the color of the penis can darken. This is not an immediate effect, but if you use the penis pump daily, and especially if you use it at higher pressures, whatever your natural skin color is, you will see that become darker in the area of penis. Most, if not all of that, will reverse and go back to your natural skin color if you stop using the pump, or use it less frequently. This is a known side effect of using the pump every day.

    Swelling

    The other thing that can occur is immediately after using the pump, there can be some edema, or swelling. The fluid from inside the penis can extrapolate out of the intravascular space, and when you take the pump off, not in the erect state, but when the penis becomes flaccid again, then you’ll see some puffiness. This is a normal thing and does not mean that you’ve damaged your penis, and it will go away usually within a few hours. Interestingly while it’s there, if you have another erection, the penis will be somewhat larger than your normal erection because of that edema that lives partly just under the skin. That gives a nice little extra … Not a lot, but somewhat larger erection. Again, that’s short lived and not permanent, but it could happen to some extent almost daily if you’re using higher pressures.

    Penis Pain

    Another reason that you may not want to use the pump is that it can hurt. The way you avoid this is … We’ll talk about in more detail about the specific protocols, but one of the ways to avoid it, I’ll tell you right now, is just to use a lower pressure in the beginning, just like if you were stretching for yoga or something. You would start with a little bit of a stretch, and then as your muscles relax, you would increase the intensity. Basically everything that I’m going to tell you about how to do this should avoid the pain.

    Decreased Function

    Some people call this “turtling.” Your penis says, “Nope, I need to take a break.” Your penis may feel rubbery, or puffy, and seem like it’s tired.  The answer is to give it a rest. Don’t use the pump for a week. If you can, avoid ejaculation for 2 weeks. Let your penis recover. You can over train the muscles. You can over train the penis. With any training there is danger of damage. With any training. Some would make the case that when you lift weights you cause damage, then when the muscles heal, they heal back stronger. To a certain extent, this is what happens when you use the penis pump. So, if erections, seem to become less firm, or if sensation seems to go down, this would be like over training with weights and the answer is to take a break. When you recover back to your baseline/normal function, then you can go back to pumping (with your doctor’s permission) at a lower pressure and/or lower frequency or time in the pump.

    The good news is that when you follow the entire Priapus Shot® procedure the PRP should help your penis recover just like PRP can help muscles and tendon and collage and nerve recover in other parts of the body.

    A Date with Your Penis

    Another reason that many people resist using a penis pump is that it just takes time. We have time just making time to eat one some days, and having an appointment with a pump for 10, 15, 20, 30 minutes a day seems like a big deal. I’ll tell you right now, the chances are you won’t do it on a daily basis unless you do this along with something else. If there’s a trigger. For example, if you watch the news every night and you make it a point to use the penis pump while you watch the news, then you’re much more likely to use it than if you just think you’re going to have a 30 minute appointment with your penis everyday.

    Some people are motivated enough to do that, but even when it comes to something as simple as walking, where we know it saves us from death, most people don’t make time to do it on a daily basis, even though they know it helps prevent heart disease and helps with sex and intelligence and depression and many other things, bone mass. Most people won’t make time to do it because they’re rushed for time. They aren’t sleeping enough, they’re working too much, their family needs them. I would advise you that if you want to see benefit from a penis pump, that you make it triggered … Your appointment to do this triggered by something else. It’s the thing you do right before you go to sleep while you read a book, or it’s the thing you do when you take a bath every night, or right before you take a shower, something like that.

    Caught with Your Penis

    Another reason for not doing is just embarrassment. Many people are … This idea of using contraption, people knowing that they might somehow want to make their penis work better or bigger. You would think there would be something that you would be proud of, and some men are. Just like they are proud that they workout everyday, they are proud that they use their pump everyday. Most men are not. It’s something that’s private and it’s definitely something you don’t do like you would with friends around the television watching the Super Bowl, for example. Most neighbors don’t come around and sit around the living room and pump their penis. There is a certain mystery and there’s some sacred … It’s a sacred subject, sex is. It’s the thing that you do behind the closed doors, including taking care of your sexual parts.

    I don’t mean to imply that this is something you broadcast on Facebook tomorrow, but the idea that you should be so embarrassed by it that you feel shamed if your lover knows that you do this is perhaps something that’s worth reconsidering. If you could have an honest discussion with your lover that goes something like the following dialogue then you can leave the shame where it belongs, which is out of your life.

    Here’s the possible conversation…

    I want to let you know that I've been reading ... I don't want you to think something freaky is going on. I've been reading about ways to keep my body healthy, not just my brain and my muscles and my heart and my digestion, but my sexual organs. One thing that's been noted is that using a penis pump can help with erectile function and blood flow and help a straight, functioning penis throughout my life if it's done intelligently, and just wanted to let you know that this is something that I'll be doing for a few minutes everyday. Don't want you to feel threatened by it, it doesn't mean that I have developed some real fetish and in love with this device more than I am with you, but it's just something that I do. Sort of like stretching out before I do a 100 yard dash.

    If your lover has a problem with that, then there may be some relationship problems that are much more serious than the idea of pumping your penis.

    Wasting Time?

    Another reason for not using the penis pump—“What if I do all of this and it doesn’t work?”

    When people say I did the Priapus Shot® and it didn’t work, or I used the penis pump and it didn’t work, then my next wondering is how did you define working? Did you expect to grow your penis three inches longer? Were you trying to correct Peyronie’s Disease and get the angle of the bend in your penis to a place where it’s usable? Were you expecting to become arrow straight and like it was when you were 16 years old?

    The truth is that nothing works all the time—even antibiotics. You may think our antibiotics are so amazing that no one dies from infection. The real statistics are that people who have pneumonia severe enough to go into the hospital, 1 in 5 of them (20%) die in the hospital because our antibiotics “don’t work.”

    But, because 20% of people in the hospital die with pneumonia die, no one says, “antibiotics don’t work.” Antibiotics do kill bacteria and most of the people who would have died from pneumonia 100 years ago now get well and go home. But in some people, other factors cause the person to die from the pneumonia even with the antibiotics: maybe their nutrition is low or they have lung disease or they have decreased immune function or problems with their heart, or maybe the bacteria is especially virulent. Many factors could prevent a person from recovering from their pneumonia, but that does not mean that antibiotics don’t work. Antibiotics kill bacteria, but not everybody who takes antibiotics for pneumonia gets well.

    In the same way, the penis pump “works” in the people who use it; most of the time, men see changes. It’s not going to take a man who has type two diabetes and severe atherosclerosis in the iliac arteries to the point that there’s no blood flow getting to his penis, you can’t then use a penis pump and somehow force blood flow into the penis and clean out his iliac arteries. In other words, there’s a dam upstream from the penis.

    One of the reasons for not using the pump is the idea, well maybe with me it may not achieve my desired results. All I can say is that you’re right, it may not, but whatever results you achieve are going to be your best penis. Just like I know I can lift weights all day long and I’m never going to have the muscles of Arnold Schwarzenegger. Even when I was younger, I did not have that genetics, in the same way I’m not going to grow a 14 inch penis. I don’t have that genetics. I have been able to put an inch and a half onto my penis with these therapies, and at that point, it was sufficient and I just maintained what I did.

    The thing is, we live in South and Bo Jackson is a big football hero here. Won the Heisman Trophy and just ran over people in football and knocked the ball crazy in baseball. In high school, he did pushups. He had such an amazing genetic physique, he just did a bunch of pushups. In the same way, it’s easier for some people to see the benefits and taking any one part of this course in how to straighten your penis and deciding that’s the one magic thing and if it doesn’t work then it’s all hokey-ness is just not considering the whole picture.

    Fires Explain Healing

    I think another analogy to consider is the analogy of a fire. If someone tells you you can start a fire by using a match and you go out in the street in front of your house and you strike a match and throw it down, you get a little flame and it’s gone. You think well, I guess I had a fire but not much really. Since you’ve never seen a fire, you go to ask another person and they say oh, you should cut down a bunch of wood and stack it up. That makes a good fire. You go chop down a tree and you chop it up and you split it and you make a big pile of wood in the street in front of your house, but no fire. You think well wood doesn’t help a fire. Someone else tells you oh, you can put some lighter fluid, that makes a fire. You get lighter fluid and you squirt that in the street, nothing happens.

    You get my point, obviously. If someone comes along and says oh, to make a fire what you really do is you make the wood in a stack, then you put the lighter fluid, and you strike a match. You do that and now you have a fire. If someone says oh, wood, that’s worthless, that’s hokey, that’s a big scam, wood doesn’t make a fire. What they’re really saying is I’m looking at a little sliver of it and I haven’t figured out about my particular body what’s missing that I’m not getting what it is I’m trying to do, or are my expectations out of reach and I’m thinking I’m going to start this blazing Dante’s inferno with a match and a few twigs. Hopefully that helps you understand whatever results you achieve, that’s going to be your best penis, and your best penis and your best health, mental, physically, spiritual, and penile health is all going to be achieved when you consider the whole picture. When you’re not getting the results that you desire, don’t be like the guy who decides firewood doesn’t work because he’s trying it as a stand alone, say well this didn’t work the way I’m using it, what else do I need to do about how I’m using it and what else I’m doing to make it work?

    Now let’s get to the how. First the equipment that you’re going to need. You’re going to need something that creates a vacuum. There are electric pumps, and there are hand pumps. If you got the privacy, an electric pump is better because you can just set it and forget it. You set it, it takes a minute or two to get things situated, you set the pressure where you want it, and you watch the news or you read your book or you listen to your podcast.

    The hand pump, I think you pump it up to the pressure you desire and forget about it, but unfortunately there’s hardly ever a perfect seal, so you have to pump it now and then periodically, about every few seconds usually. It’s a distraction to doing something else. It’s nice in that they’re more portable and a hand pump is quiet, so it’s something you can throw in your bag when you travel and something you can do in the restroom without someone wondering what’s the motor in there while you’re taking a shower. With this, you can be quiet about it.

    Anyway, you’re probably going to want both, an electric pump and a hand pump. For the … By the way, if embarrassment is a thing and you just don’t want to have a discussion about this, then a hand pump that you put under a towel and take with you to the restroom is a nice way to get around that. Most people are not going to bother you on the john. Even if you don’t want to take a shower, if you just get to the stall or your private place where you go to the restroom and you lock the door and use your pump, they may just think you have constipation that day because you’re in there for 15 minutes.

    Next you need the tubing and the cylinder. The cylinder, there are two ways you can think about. One, sort of a one size fits all with a phalange at the base of the cylinder that expands and contracts based on the size of the penis. Your penis will change size as you use the pump, so that expands. I find those to be the least comfortable, that expansion puts pressure on the base, like a rubber band around the base of your penis. I find that to be the least comfortable but many people like them and get nice results. What I like better is a cylinder that’s sized for the penis so that it starts off somewhat larger from your flacid penis, but then when your penis is expanded by the pump, it comes close to being the same size as the cylinder, and at full expansion your penis basically fills the cylinder. You can change the size of that cylinder as your penis might grow.

    You have a cylinder, you have a pump, you have the tubing between the two. I prefer a tubing that you can disconnect that has an actual valve on it, but that’s not necessary. It’s interesting, one of the dentists who came to see me went to the auto repair store and bought a brake repair kit, used the pump on that because it’s very substantial, and connected that to the tubing that goes to the cylinder.

    The lubrication that you use, that can be petroleum based like a KY jelly. People are all into it has to be water soluble. Why? I don’t know that it needs to be water soluble, you just wash out the tubing. I prefer a vegetable based, there are some creams that are made that are based on coconut oil or Vitamin E. If you want just get you some coconut oil in the cream type consistency at the grocery store.

    Then another nice tip that one of my patients taught me who achieved wonderful results is just taking some water, not very much, a tablespoon or two, warm water, putting that in the cylinder, and then pressing the cylinder against your body. That holds the water in, and you keep the tubing elevated above the water. The water sort of acts both as a lubrication and a warming agent that is really nice. It gives, I think, a little better seal, but it’s a little sloppy so you have to have a towel or something there. It’s going to drip everywhere if you don’t.

    Then what else. Let’s talk about how you do this thing. We’ve talked about the equipment, so how do you do this. First, it helps if you’re semi-erect, but you don’t have to be. It helps if you know you’re not going to be disturbed. It’s a little bit awkward to suddenly have to take the pump off because someone walks in the room or whatever that you don’t want them to be shocked by what you’re doing. So a locked door, and then you want to put the tubing firmly against your body, the tube that your penis goes into, and aim it more horizontal. If you aim it up, which is normally how your erection would go, it makes the seal break and your testicles can be pulled up into the tubing. The tube that your penis goes into should be at a right angle to your body. Pull your testicles down out of the way. You have whatever lubricant you’ve chosen there, and then you start pumping.

    Pump to the place where you feel a mild pull, maybe a very mild discomfort but not pain. Most people when they first put their penis into the pump, that happens somewhere around minus five inches of mercury. On the penis pumps, it’s usually the scale on the outside, and it will be the greater pressures. There’s usually two scales, there’s millimeters and there’s inches. The inches will be at a greater pressure. It’s usually about, on most penis pumps, it’s about a fourth of a way on the scale. I have some people who look at the wrong scale and they’re just not going up high enough. It’s minus five inches of mercury. If it starts to feel tight to you at three or four it doesn’t really matter, just whatever that is.

    Then set a timer and keep it there, you’ll notice that it starts to feel less tension, just like if you were stretching your leg or something. Then as you go, just increase the pressure. The goal is to make to at least seven, preferably up closer to ten by the time you reach the end of the session. Preferably for the last five minutes of a 10-15 minute session you’re up closer to ten. I think it’s better if you keep it at ten or less. Some of the old school people tell me they would go to 15. One of the guys that got really nice results with me went minus 15 twice a day. He only did that three times a week, so he used a higher intensity with a less frequency. Sounds like a workout routine, doesn’t it. You do three sets of five everyday, or you do heavy duty hard weights twice a week. All sorts of theories about how to lift weights. It’s the same principle isn’t it. You put physical stress on the tissue, and then you allow recovery, which is why the Priapus shot helps so well, because just like Priapus helps with recovery of muscles, it can help with what you’re doing for the penis.

    I think it’s worth saying here that combining the two, there is some synergy. Was Arnold Schwarzenegger big because he lift weights or because he did steroids? In Arnold’s day, you could go to the pharmacist and he would just give you testosterone and the anabolic steroids were like antibiotics. There were not laws passed against them, the pharmacists would just give it to you if you just asked them for it. The veterinarians would give you all these veterinarian medicines. Arnold doesn’t try to hide it, back in the day that’s just what they did. They also lifted weights like gladiators. Had he lifted weights without the steroids, he would have been in amazing physique, but doing the two together so he could lift like a gladiator and then recover enough to lift the next day, that’s exactly the principle we’re applying. Some people will say well a penis grew an inch with the Priapus shot, but was it from the pump or was the from the PRP? Well, was Arnold big from lifting weights or from taking steroids? If you want to be a purist, just use the pump, but if you want to have your best penis, use the pump combined with the Priapus shot. That’s just how it goes.

    Back to how to do this thing. You put the cylinder there, you apply pressure, you try to work it up to minus seven to ten, and you want a total of 10 minutes. Take a five minute break where you let your penis recover, sort of massage it, get the blood flow back into it, try to avoid masturbating, you want to try to keep your hormones high. At least try to avoid having an ejaculation because those hormones are going to help you grow your penis. I’m not saying you can never ejaculate, but try to make penis pumping about growing your penis and avoid ejaculating if you can.

    Take a five minute break, and then you apply the pump again for another 10-15 minutes. That’s it. Take the pump off, or the cylinder off. If you want, you can have a band that goes around the top of your penis and the under side of your testicles to help hold the blood in your penis for the next hour or so.

    Let’s see, what else can I tell you? That’s how you use the thing. I think that’s enough for now. I hope this is helpful to you. Penis pumping is almost like weights were back in the 50s and 60s. I came up, I was born in 1960 and had an uncle, my mom’s brother, he had an amazing physique. He would train at the YMCA. There were no gyms like … In those towns like Birmingham where I grew up, there were no fancy weight training gyms. You had the YMCA, which was sort of like a mission. It was started as a Christian mission for people who didn’t have another place to live. There were rooms there. People who just got out of prison would go stay there, like the Salvation Army or whatever homeless mission you have in your town. It was part of the United Way, and then they became the weight training part of it became more prominent, and the place to stay part of it because eventually phased out, which may be unfortunate.

    Anyway, that was where you trained. That’s where you lifted weights. The coaches, many of them, most of them actually thought that lifting weights made you muscle bound and clumsy. Even the doctors thought that the weightlifting body builders were just bloated from the steroids, they weren’t really stronger. Amazingly it wasn’t until the late 1980s that the research came out showing that anabolic steroids actually make you stronger. All that to say, there was this underground about lifting weights. When I at 15 in 1975 went to a huge bookstore in Birmingham looking for a book on weight training, there were only two. One by Arnold Schwarzenegger called Education of a Body Builder, and another by Frank O’Clumbo who was one of his training partners and a friend from Italy. That was it. There’s whole shelves of weight training books now, right? The muscle and fitness magazines were little black and white things.

    All that to say, it could be, just maybe, that penis pumps are something similar. The people doing it are ahead of the physicians by a long way, and the research over the next few years will catch up with what the people are noticing that are using a pump. I don’t think, in my experience, you can take someone with a three inch erection and grow it into a ten inch erection. Maybe that’s possible, I don’t know. Maybe that’s a full time job to do something like that. I’m less inclined to think that sort of thing is possible. I think it’s more of a percentage thing. In that same way that Bo Jackson and Arnold grew in proportion to their genetics, I think the same thing applies to the penis. In my experience of seeing it easier for a man with a seven inch penis to grow it to eight, it’s actually fairly routine if he’s using the pump and a Priapus shot, or for five and a half to grow to seven. It’s more difficult for three to grow to four, or four to grow to five. Although it can happen, I think it’s more difficult.

    The interesting this is that even in the guy with the seven inch penis, it’s not 100%. That is the most frustrating part of this. When I talk with people who are doing other things with tissue regeneration, for example I recently did a lecture in Venice and shared the podium with one of the world experts in hair regrowth. We talked after his lecture, because in his lecture he said that he was not able to predict who would grow hair and who would not consistently. He could do blood tests and try to perdit. In other words, he wasn’t sure what the complete formula was for making the fire in everybody. Maybe there are ingredients that are missing in some people that we don’t yet know how to identify.

    Believe me, I am thinking about this a lot. I’m researching it, I’m reading about it, I’m going to classes trying to see what people are talking about. I think that you’re going to see great strides made. I’m giving you in this course what I think works best for helping the best formula for growing a harder, straighter, bigger penis. I think you’ll see that science change. I’m grateful and honored that you’re interested in these ideas. I encourage you to read and study and stay in contact with me, and contact me by email. You can post things, it’s really a better way to post to the blogs. Contact the doctors that provide the Priapus shot. They’re being updated by me on a regular basis on the science. We have amazing, phenomenal, amazing urologists in our group doing research in this arena. Much of what they’re finding scientifically is not in the research yet. Usually what happens is people notice things, they might talk about it, they may not, they publish it in the research literature like the New England Journal and Journal of Sexual Medicine.

    Save

    Save

    Save

    Save

    Save